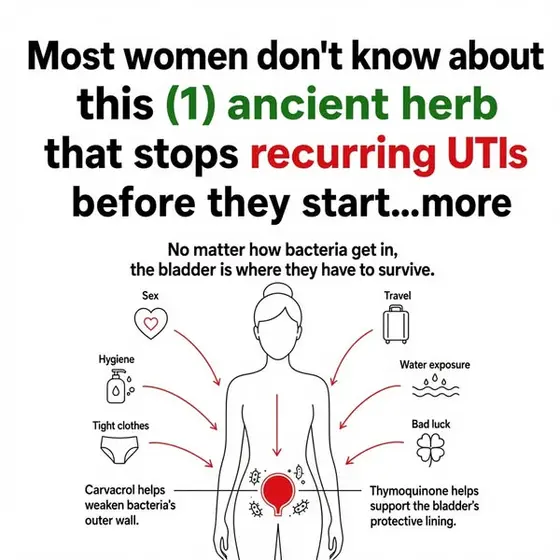
UTI Cycle Reset Facebook ad creative
orynwell.com
Build A Bladder Bacteria Don’t Want
Learn more

UTI Cycle Reset Facebook and Instagram ad

UTI Cycle Reset ran this image ad since Jun 23, 2026, 3 days so far, targeting United Kingdom.

First seen
Jun 23, 2026
Running for
3 days
Format
Image
Call to action
Learn more
Niche
Health and supplements
Countries
1 targeted
Page likes
4

Ad copy

I've been an OB-GYN for 27 years. And if your UTIs keep showing up after sex, your antibiotics seem to give you less peace every cycle, and your doctor keeps telling you to “just pee after sex” or “try a stronger prescription”... I’m about to tell you why the usual post-sex UTI advice may be missing the real problem. And by the end of this, you're gonna be pissed. My name is Dr. Sarah Harlan. Board-certified OB-GYN and women’s urinary health specialist. Twenty-seven years helping women with chronic urinary discomfort, bladder infections, and recurring UTI patterns. Over 9,800 patients. And I’m breaking ranks with my own profession to tell you this. Because there are three things happening right now: One — Most women are told to obsess over what caused the UTI after intimacy. Sex. Partner hygiene. Not peeing fast enough. Wiping. Tight jeans. Dehydration. Bad luck. But once the bacteria reach your bladder, the real question is simple: Can they survive there? Two — Most UTI products were never built to answer that question. AZO masks the burning. Cranberry and D-Mannose try to stop bacteria from sticking. Antibiotics may be needed when things get bad, but they are not built as a gentle daily bladder defense. Three — The UTI industry makes money every time one intimate night turns into another bladder emergency. Another appointment. Another prescription. Another orange-pee pain pill. Another “keep this in your purse just in case.” So let me tell you what happened with one of my patients, because her story is going to open your eyes to how messed up this really is. Her name was Claire. 48 years old. For YEARS, and I mean like five straight years, she was dealing with this. Her infections? They almost always seemed to show up after sex. At first, it was one UTI after a normal weekend with her husband. A straightforward case. Burning, urgency, frequency. She came to me early — week two. I told her we’d handle it. No big deal. I prescribed trimethoprim-sulfamethoxazole. Standard first-line antibiotic. “Take the full course,” I said. “Be consistent.” She was consistent. She took every single pill at the exact same time every morning for seven days. Religiously. Never missed a dose. And you know what happened? The infection didn’t stay gone. Six weeks later, after another intimate night, the same burning. The same urgency. The same pressure building in her lower belly that told her she had maybe twenty minutes before it became unbearable. And then it accelerated. The second course seemed to hold for five weeks. The third for four. By the end of year two, she was getting a new bladder scare every three weeks — usually right after she had finally started feeling normal again with her husband. Each round gave her less peace than the last. She stopped booking overnight trips. Stopped committing to anything more than an hour from home. Started mapping bathroom locations before she went anywhere — restaurants, malls, her daughter’s school events. She told me once: “I plan my entire life around where the nearest bathroom is.” And the fear? It wasn’t just inconvenience anymore. She was terrified of intimacy. Not because she didn’t love her husband. But because every normal night together felt like the start of a countdown. She had a 9-year-old daughter who had started noticing that “Mommy always has to leave early” — and Claire would change the subject and hold back tears, scared this was just her life now. And here’s what makes me sick to my stomach: I was the doctor she trusted. Multiple visits. Year after year. Thousands of dollars in appointments, prescriptions, antibiotic rotations, specialist referrals... the whole nine yards. And you know what I kept telling her? “The antibiotic needs more time.” “Try switching to nitrofurantoin.” “It’s manageable. We just need to find the right combination.” “Be more consistent with hydration.” “Make sure you pee after sex.” BE MORE CONSISTENT. This woman was doing everything right. She was taking every antibiotic course to completion. She was drinking water. She was peeing after sex. She was wiping the right way. She was avoiding bubble baths. She had cranberry in her cabinet, D-Mannose in her kitchen, AZO in her purse, and a backup prescription in her travel bag. And I was still making her feel like she wasn’t doing enough. But here’s where it gets worse — and this is the part that haunts me now. I switched her to a different antibiotic. Then another. Then I added a low-dose daily suppressive antibiotic. Then D-Mannose powder. Then a probiotic protocol. Then cranberry extract. Then AZO every time she felt symptoms coming on. Then a urologist referral for cystoscopy. You know what happened? The bladder scares kept coming back. The suppressive antibiotic gave her a few quiet months — then the symptoms came back the moment she stopped. The D-Mannose helped a little at first, then did nothing. The probiotics “helped a little with digestion” but didn’t change the UTI pattern. The cranberry extract was “like taking sugar pills at this point.” The AZO turned her urine orange and masked the burning for a few hours. And the urologist? After the cystoscopy found nothing structurally wrong, he told her: “Some women are just prone to recurrent infections.” I watched this woman — who did everything I told her, spent thousands of dollars, followed every protocol — get worse. Not better. Worse. And I didn’t understand why. Until a 63-year-old bladder researcher taught me more about recurring UTIs in 20 minutes than I learned in nearly three decades of OB-GYN training. October 2024. San Francisco. American College of Obstetricians and Gynecologists Annual Meeting. I was calculating in my head whether I had time to use the bathroom again before the next session. Because at 54, my own post-intimacy UTI cycle had started fourteen months earlier. And nothing I had been prescribing to patients for 27 years was giving me peace either. Worse — the fear was getting stronger every cycle. The gap that had started at eight weeks was now down to three. I had a prescription in my purse at all times. I knew every bathroom in every conference center I had visited that year. And I had started doing something I hated admitting. I had started avoiding intimacy too. Not because I wanted to. Because I was scared of what might happen the next morning. That’s when I saw her. Dr. Evelyn Santos. 63 years old. Presenting for two hours straight. No distraction. No urgency. No quiet slipping out mid-session to find a bathroom. Moving through the day the way a person moves when she is not calculating distances and timing with every step. She had mentioned in her presentation that she had dealt with chronic recurring UTIs herself for years and finally changed her approach. I had to know how. I walked over. “Excuse me — I’m an OB-GYN. I’ve been dealing with recurrent UTIs for fourteen months. They often seem to happen after sex. The gap between scares feels like it’s getting shorter. I’ve tried everything I prescribe to patients. Nothing is breaking the cycle.” She smiled. The kind of smile that knows something you don’t. Then she asked me one question: “Dr. Harlan, are you still thinking about this as a ‘what caused it after sex’ problem?” I froze. Because that was exactly how I had been thinking about it. Sex. Partner hygiene. Not peeing fast enough after sex. Not enough water. Tight clothes. Bad luck. She looked at me and said: “That’s the trap. You can spend years trying to figure out how bacteria got in. But once they reach the bladder, the real question is: why are they surviving there?” My stomach dropped. Then she said something I will never forget: “You’re treating every flare-up like a new accident. But in many recurrent sufferers, the bladder has become too easy for bacteria to survive in.” She looked at me steadily. “The problem isn’t that your patient is dirty. It isn’t that she didn’t try hard enough. It’s that her bladder environment is not defended the way it should be.” Then she said: “You’re fighting every spark after the smoke alarm goes off. But you’re not making the room harder to burn.” She gestured to an empty table. “May I show you something? It will take twenty minutes. But it will change how you understand this completely.” What she taught me in 20 minutes changed everything. She drew a simple diagram on a napkin. “Your treatment model treats every UTI like a separate event. So you clear the active infection. You tell her to drink water. You tell her to pee after sex. You give her cranberry to block sticking. You give her AZO to numb the burning.” She tapped the napkin. “But look at the pattern. The same woman keeps getting hit again and again. Different triggers. Same final destination.” The bladder. Then she drew a circle around it. “It doesn’t matter if the bacteria came from sex, partner hygiene, wiping, water exposure, underwear, or bad luck. Once they reach the bladder, they all end up in the same place.” Then she drew two words inside the circle: SURVIVE HERE. “That’s the part most UTI products ignore.” Now pause for a second. You know what’s insane? We learned in medical school that the bladder has a natural protective lining. We learned that bacteria need to stick, survive, and grow before a UTI takes hold. We learned that some bacteria become harder to deal with after repeated exposure to antibiotics. We learned that recurrent UTI sufferers are not always doing something wrong. We know this. And yet we keep giving women the same advice: Drink more water. Pee after sex. Try cranberry. Take AZO. Take another antibiotic. Come back if it happens again. And when it does happen again? We repeat the same loop. Again. And again. And again. Here’s what’s actually happening underneath: Your bladder is supposed to have a natural inner lining. Think of it like a slick protective shield. When that shield is strong, bacteria have a harder time sticking to the bladder wall. They have a harder time settling in. They have a harder time turning one exposure into another full-blown scare. But in a lot of women with recurring UTIs, that lining can become worn down. That means the same small amount of bacteria that another woman’s body shrugs off can become a problem for you. That’s why it can feel so unfair. Your friend can forget to pee after sex and be fine. You do everything right and still wake up with that familiar burn. That doesn’t mean you’re dirty. It doesn’t mean you failed. It may mean your bladder’s natural shield needs support. And here’s the second part: Bacteria are not helpless. Some bacteria are tougher than others. Some learn how to survive the same tools we keep using. That’s why the antibiotic that worked the first time may not feel as reliable after the fifth, sixth, or seventh round. So the real issue is not just “how do we numb the pain?” It’s not just “how do we block sticking?” It’s not even just “how do we kill what’s there right now?” The deeper question is: How do we help your bladder become a place where bacteria have a much harder time surviving in the first place? That was the sentence that changed everything for me. Because Claire’s problem wasn’t compliance. My problem wasn’t compliance. Thousands of women’s problem isn’t compliance. The problem is that most UTI products are built for the wrong job. AZO can numb the burning, but it does not touch the bacteria. And it can turn your pee orange. Sometimes neon orange. Sometimes “I just stained the toilet at urgent care” orange. D-Mannose can help bind certain bacteria, but it does not kill them. Cranberry can help reduce sticking, but it does not rebuild the bladder’s natural shield. Probiotics can support general balance, but they are not a direct bladder defense. Antibiotics can be important when you have an active infection. I still use them when they are needed. But antibiotics are not a daily plan for women who are tired of every flare-up becoming an emergency. They are for when things get bad. But Claire didn’t want to keep getting there. Neither did I. So Dr. Santos showed me the actual approach I had been missing. It involved three things happening together: 1. A bladder kill-zone — support that helps make the bladder a harder place for unwanted bacteria to survive once they arrive. 2. Resistance-aware defense — a mechanism that does not depend on bacteria being weak, new, or easy. 3. Bladder lining support — helping the bladder’s natural inner shield do the job it was supposed to do all along. That is when she brought up two compounds I had been ignoring for years: Carvacrol from oregano oil. And thymoquinone from black seed oil. Not random “herbal wellness” fluff. Not a cheap oregano capsule from a health store. Not cranberry with a prettier label. Carvacrol is the active compound in oregano oil that can disrupt the outside wall of bacteria. In simple terms? It helps break open the bacteria’s armor. Thymoquinone is the main active compound in black seed oil. And it supports the bladder’s natural protective lining — the layer that helps keep bacteria from sticking in the first place. Together, the idea was simple: Bacteria arrive. They meet a bladder environment that is harder to survive in. And the bladder lining gets support so it is less exposed next time. Not another orange-pee pain pill. Not another “just wait for the antibiotics to kick in.” Not another emergency-only patch. A daily bladder defense. And here’s the part that made my blood boil: The women’s health industry knows women are tired. We know they are keeping supplies in their cabinet, purse, and travel bag. We know they are sitting in meetings while silently counting the minutes until they can pee again. We know they are scared when they feel that first little sting. We know some women are avoiding intimacy because they are tired of paying for it the next morning. But what do we keep handing them? A pain dye that stains everything. A cranberry bottle that blocks but doesn’t kill. D-Mannose that may help some women but does not solve the full problem. Another antibiotic. Another “come back if it happens again.” See how that works? The system is designed to manage the next flare-up. Not help women stop living in fear of the next one. Now here’s the problem I ran into... Most oregano supplements are garbage. I tried a cheap oregano capsule. Low potency. No clear carvacrol amount. Smelled awful. Tasted worse. Gave me oregano burps. Did nothing for my bladder confidence. I tried a “urinary health” probiotic. Nice bottle. Soft marketing. No direct bladder kill-zone support. I tried cranberry again. I tried D-Mannose again. I tried the same things I had told patients to try for years. And I kept thinking: If this worked so well, why are so many women still getting UTIs after intimacy? Why are so many women still afraid of the next morning? Because here’s the thing: A generic cranberry capsule is NOT the same as a true daily bladder defense. And a weak oregano capsule is NOT the same as a high-potency oregano oil softgel built for women who are tired of the UTI treadmill. Most supplements fail at one of the three requirements. Too weak. Wrong target. Bad format. Hard to take every day. Orange pee. Bad taste. Mess. Stomach issues. Or they only help when you are already miserable. Until I found Orynwell. They had an Oregano + Black Seed Oil softgel. Not a generic multivitamin. Not a low-dose oregano powder. Not a cranberry pill pretending to be a breakthrough. A dual-action bladder defense formula. With the two compounds I was looking for: High-potency oregano oil standardized for Carvacrol. Black seed oil with Thymoquinone. And the format mattered. Two softgels a day with food. No orange pee. No bad taste. No drops under your tongue. No staining. No “ugh, I have to take that thing.” Just two softgels with breakfast. Thirty seconds. Done. When I dug into the formulation? It made sense. Orynwell delivers 6,000mg of high-potency oregano oil equivalent from a 20:1 extract, with 165mg of Carvacrol per serving. It also includes 200mg of black seed oil. That means it is built around the two things recurrent sufferers actually need: Make the bladder harder for bacteria to survive in. Support the protective lining bacteria try to stick to. They weren’t just selling “urinary health.” They understood what most products miss. They knew why women keep saying: “I did everything right and it still came back.” They knew why so many women are tired of being told: “Some people are just prone to them.” They knew why “just pee after sex” feels insulting when you are already doing that every single time. And here’s where I had to face what I had done to my patients. When Claire was filling antibiotic prescriptions from me? Money every month. Plus the D-Mannose. Plus the probiotics. Plus my office visits every 6-8 weeks. Plus the urgent care trips when symptoms hit on weekends. Plus the cranberry supplements. Plus the AZO she cycled through hoping one would finally work. She was spending thousands of dollars a year. Every single year. Just to manage a cycle that kept coming back. The Orynwell softgels? A fraction of what she had been spending on things that only helped part of the problem. Designed to support the bladder before the next flare-up takes over her life. Carvacrol to help create a tougher bladder environment for unwanted bacteria. Thymoquinone to support the bladder’s natural protective lining. Two softgels with breakfast. No orange pee. No staining. No “keep wearing dark underwear just in case.” I started using them myself first. Week 2: The constant low-level urgency — that background pressure I had stopped noticing because it had become my normal — began to quiet down. Not overnight. Not like a pain pill. More like my bladder stopped yelling at me all day. Week 4: I reached the point in my cycle where I would normally start worrying. That little voice in my head would usually start: Is this the day? Is that the first sting? Should I call in a prescription now? But nothing started. I didn’t trust it yet. But I noticed I had not checked the bathroom location once that morning. Something I had not done in fourteen months. Week 8: I went to a conference — full day, back-to-back sessions — and did not calculate bathroom access once. No silent panic. No sitting near the aisle “just in case.” No prescription in my purse feeling like a life raft. The gap between my last scare and that morning was already longer than any gap I had had in over a year. Week 12: Full assessment. The urgency was gone. The dread was gone. And for the first time in over a year, I stopped treating intimacy like the start of a countdown. That sounds small unless you’ve lived it. But if you’ve ever felt scared after sex because you were waiting for burning, pressure, urgency, orange pee, leaks, stains, or another doctor call... You know exactly what that meant. Then I called Claire. And every other patient I had failed. “I need to tell you something. I was treating your bladder like it only needed emergency help after the burning started. But for recurring sufferers, the bladder needs daily defense before bacteria get the chance to take over. I didn’t understand the difference. But I do now.” Claire, Week 6: “Dr. Harlan, I just hit six weeks without a scare. That hasn’t happened in three years. And for the first time since this started, I didn’t wake up after sex checking for that first burn. I didn’t even think about it until I realized I wasn’t thinking about it.” Before: Bladder scares every few weeks. Multiple antibiotic courses. Cranberry. D-Mannose. AZO. Doctor visits. Bathroom mapping. Purse full of backup products. Avoiding intimacy. After 6 weeks: No new flare-up. No emergency trip. No orange pee. No waking up the next morning scanning her body for symptoms. The gap that had been collapsing for years finally held. She drove four hours to her college roommate’s birthday weekend last month. First overnight trip in two years. No backup plan. No pharmacy location mapped. No calculating whether she was too far from home. She called me from the road on the way back. “I didn’t think about my bladder once the entire weekend. Not once.” That was the moment I knew. She did not just get symptom relief. She got mental relief. She booked a trip to Europe with her sister for next spring. Something she had said no to three years in a row. And she told me something else quietly: “I feel like I can be close to my husband again without bracing for what comes after.” She got her life back. This is the daily bladder defense most women have never been told about. Because the second your bladder becomes a harder place for bacteria to survive, everything changes. You stop treating every tiny sting like a full emergency. You stop keeping three different products in your purse. You stop wondering if sex, jeans, travel, dehydration, or “bad luck” is about to ruin your week. You stop asking: “What did I do wrong this time?” Because maybe you didn’t do anything wrong. Maybe your bladder just needed better defense. Now here’s what I need you to understand about timing: The urgency is real. Your bladder does not wait until you are ready. One small scare becomes a weekend ruined. One weekend becomes another doctor visit. Another doctor visit becomes another prescription. Another prescription becomes another month of wondering what it is doing to your gut, your yeast balance, and your long-term resistance. And the fear builds. If you are at one or two UTIs a year right now — this is the time to start supporting your bladder before the pattern gets worse. If you are already dealing with symptoms every few weeks — you already know how fast one normal morning can turn into “I need to find a bathroom right now.” If you are reading this and the gap between scares is measured in weeks, not months — act now. Because this cycle does not just hurt. It shrinks your life. It makes you say no to trips. No to long car rides. No to sex. No to being close without fear. No to light-colored pants. No to sitting through a movie. No to sleeping through the night. No to feeling normal in your own body. And if you are someone who has been dealing with this — burning, pressure, constant urge to go, the dread, the calculating, the bathroom mapping, the fear after intimacy — and nothing has worked? It is not because you are dirty. It is not because you did not drink enough water. It is not because you forgot to pee after sex one time. It is not because you failed. It may be because your bladder has become too easy for bacteria to survive in. And that is exactly what Orynwell was built to support. Orynwell has a 90-day money-back guarantee — if you don’t feel the difference, you’re not out anything. And honestly? Even if you are skeptical, try it for 90 days. Take two softgels with breakfast. Watch what happens to the gap between scares. Watch whether that background urgency starts to quiet. Watch whether you stop checking for bathrooms without even realizing it. Watch whether your purse stops feeling like an emergency kit. Watch whether intimacy stops feeling like the start of a painful countdown. That is your proof. Because the UTI industry is not coming to save you. There is too much money in the cycle: The urgent care visit. The antibiotic. The AZO. The cranberry. The D-Mannose. The probiotic. The refill. The next scare. The next appointment. A 63-year-old bladder researcher taught me more in 20 minutes than I learned in nearly three decades of OB-GYN training. It is about time I passed that lesson on. Learn More -> https://orynwell.com/pages/uti-cycle-reset-report-305 P.S. — I still tell women to see a doctor when they have active UTI symptoms. Orynwell is not an emergency antibiotic replacement. It is a daily bladder support routine for women who are tired of waiting for the next flare-up to take over their life. P.P.S. — If your UTIs keep coming back after intimacy, stop spending all your energy trying to figure out exactly how the bacteria got in. Sex, partner hygiene, not peeing fast enough, water, tight clothes, bad luck — once bacteria reach the bladder, the real question is whether they can survive there. P.P.P.S. — Claire: “Five years. Bladder scares every few weeks. Thousands of dollars on antibiotics, cranberry, D-Mannose, AZO, and doctor visits. I did everything right and it still came back. I peed after sex. I drank water. I tried to avoid every trigger. Two softgels with breakfast finally gave me a daily defense I could actually live with. No orange pee. No taste. No constant fear. Don’t wait like I did.”

Placements and targeting

FacebookInstagramAudience NetworkMessengerThreads🇬🇧 United Kingdom

More ads from UTI Cycle Reset

Full UTI Cycle Reset profile
UTI Cycle Reset
UTI Cycle Reset
+1
Inactive1 day
orynwell.com
Build A Bladder Bacteria Don’t Want
Learn more

I've been an OB-GYN for 27 years. And if your UTIs keep coming back faster every cycle, your antibiotics seem to give you less peace each time, and everything you try only helps after you’re already miserable... I’m about to tell you why the usual UTI advice may be missing the real problem. And by the end of this, you're gonna be pissed. My name is Dr. Sarah Harlan. Board-certified OB-GYN and women’s urinary health specialist. Twenty-seven years helping women with chronic urinary discomfort, bladder infections, and recurring UTI patterns. Over 9,800 patients. And I’m breaking ranks with my own profession to tell you this. Because there are two things happening right now: One — Most UTI products only step in after you are already uncomfortable. After the burning starts. After the urgency takes over. After you are already checking bathrooms, cancelling plans, and wondering if this is about to become another full-blown bladder scare. AZO can help numb the burning. Cranberry and D-Mannose try to help once bacteria are already part of the problem. Antibiotics may be needed when things get bad. But none of these are built as a gentle daily way to support your bladder’s own defense before the next flare-up takes over your life. Two — The UTI industry makes money every time your bladder scare turns into another emergency. Another appointment. Another prescription. Another orange-pee pain pill. Another “keep this in your purse just in case.” So the system keeps you managing the next flare-up. Not supporting your bladder before the next one begins. So let me tell you what happened with one of my patients, because her story is going to open your eyes to how messed up this really is. Her name was Claire. 48 years old. For YEARS, and I mean like five straight years, she was dealing with this. Her infections? It started with one UTI in the spring. A straightforward case. Burning, urgency, frequency. She came to me early — week two. I told her we’d handle it. No big deal. I prescribed trimethoprim-sulfamethoxazole. Standard first-line antibiotic. “Take the full course,” I said. “Be consistent.” She was consistent. She took every single pill at the exact same time every morning for seven days. Religiously. Never missed a dose. And you know what happened? The infection didn’t stay gone. Six weeks later, the same burning. The same urgency. The same pressure building in her lower belly that told her she had maybe twenty minutes before it became unbearable. And then it accelerated. The second course seemed to hold for five weeks. The third for four. By the end of year two, she was getting a new bladder scare every three weeks — sometimes before she had even stopped worrying about the last one. Each round gave her less peace than the last. She stopped booking overnight trips. Stopped committing to anything more than an hour from home. Started mapping bathroom locations before she went anywhere — restaurants, malls, her daughter’s school events. She told me once: “I plan my entire life around where the nearest bathroom is.” And the fear? It wasn’t just inconvenience anymore. She was terrified it would keep happening. She had noticed the gap between infections shrinking again and she was panicking. She had a 9-year-old daughter who had started noticing that “Mommy always has to leave early” — and Claire would change the subject and hold back tears, scared this was just her life now. And here’s what makes me sick to my stomach: I was the doctor she trusted. Multiple visits. Year after year. Thousands of dollars in appointments, prescriptions, antibiotic rotations, specialist referrals... the whole nine yards. And you know what I kept telling her? “The antibiotic needs more time.” “Try switching to nitrofurantoin.” “It’s manageable. We just need to find the right combination.” “Be more consistent with hydration.” BE MORE CONSISTENT. This woman was doing everything right. She was taking every antibiotic course to completion. She was drinking water. She was peeing after sex. She was wiping the right way. She was avoiding bubble baths. She had cranberry in her cabinet, D-Mannose in her kitchen, AZO in her purse, and a backup prescription in her travel bag. And I was still making her feel like she wasn’t doing enough. But here’s where it gets worse — and this is the part that haunts me now. I switched her to a different antibiotic. Then another. Then I added a low-dose daily suppressive antibiotic. Then D-Mannose powder. Then a probiotic protocol. Then cranberry extract. Then I suggested AZO every time she felt symptoms coming on. Then a urologist referral for cystoscopy. You know what happened? The bladder scares kept coming back. The suppressive antibiotic gave her a few quiet months — then the symptoms came back the moment she stopped. The D-Mannose helped a little at first, then did nothing. The probiotics “helped a little with digestion” but didn’t change the UTI pattern. The cranberry extract was “like taking sugar pills at this point.” The AZO turned her urine orange and masked the burning for a few hours. And the urologist? After the cystoscopy found nothing structurally wrong, he told her: “Some women are just prone to recurrent infections.” I watched this woman — who did everything I told her, spent thousands of dollars, followed every protocol — get worse. Not better. Worse. And I didn’t understand why. Until a 63-year-old bladder researcher taught me more about recurring UTIs in 20 minutes than I learned in nearly three decades of OB-GYN training. October 2024. San Francisco. American College of Obstetricians and Gynecologists Annual Meeting. I was calculating in my head whether I had time to use the bathroom again before the next session. Because at 54, my own UTI cycle had started fourteen months earlier. And nothing I had been prescribing to patients for 27 years was giving me peace either. Worse — the fear was getting stronger every cycle. The gap that had started at eight weeks was now down to three. I had a prescription in my purse at all times. I knew every bathroom in every conference center I had visited that year. That’s when I saw her. Dr. Evelyn Santos. 63 years old. Presenting for two hours straight. No distraction. No urgency. No quiet slipping out mid-session to find a bathroom. Moving through the day the way a person moves when she is not calculating distances and timing with every step. She had mentioned in her presentation that she had dealt with chronic recurring UTIs herself for years and finally changed her approach. I had to know how. I walked over. “Excuse me — I’m an OB-GYN. I’ve been dealing with recurrent UTIs for fourteen months. The gap between infections feels like it’s getting shorter. I’ve tried everything I prescribe to patients. Nothing is breaking the cycle.” She smiled. The kind of smile that knows something you don’t. Then she asked me one question: “Dr. Harlan, are you still waiting until the burning starts before you support the bladder?” I froze. Because that was exactly what I had been doing. AZO after the burning started. Cranberry after the worry came back. D-Mannose after she felt that first familiar pressure. Another antibiotic after things got bad. Every solution I gave her was reacting to the flare-up. But none of it was helping her bladder build the daily defense it needed between scares. She looked at me and said: “That’s the trap. You keep treating every flare-up after it starts. But for recurrent sufferers, the bladder needs support before the next one begins.” My stomach dropped. Then she said something I will never forget: “You’re fighting every spark after the smoke alarm goes off. But you’re not making the room harder to burn.” She gestured to an empty table. “May I show you something? It will take twenty minutes. But it will change how you understand this completely.” What she taught me in 20 minutes changed everything. She drew a simple diagram on a napkin. “Your treatment model treats every UTI like a separate event. So you clear the active infection. You tell her to drink water. You tell her to pee after sex. You give her cranberry. You give her AZO.” She tapped the napkin. “But look at the pattern. The same woman keeps getting hit again and again. The same pain. The same fear. The same emergency cycle.” The bladder. Then she drew a circle around it. “Most products are focused on what happens after the problem has already started.” Pain relief after the burning starts. Cranberry after the fear comes back. D-Mannose after the first pressure hits. Antibiotics after things get bad. Then she wrote two words inside the circle: DAILY DEFENSE. “That’s the part most UTI products ignore.” Now pause for a second. You know what’s insane? We learned in medical school that the bladder has a natural protective lining. We learned that bacteria need to stick, survive, and grow before a UTI takes hold. We learned that some bacteria become harder to deal with after repeated exposure to antibiotics. We learned that recurrent UTI sufferers are not always doing something wrong. We know this. And yet we keep giving women the same advice: Drink more water. Pee after sex. Try cranberry. Take AZO. Take another antibiotic. Come back if it happens again. And when it does happen again? We repeat the same loop. Again. And again. And again. Here’s what’s actually happening underneath: Your bladder is supposed to have a natural inner lining. Think of it like a slick protective shield. When that shield is strong, bacteria have a harder time sticking to the bladder wall. They have a harder time settling in. They have a harder time turning one bad day into another full-blown scare. But in a lot of women with recurring UTIs, that lining can become worn down. That means the same small amount of bacteria that another woman’s body shrugs off can become a problem for you. That’s why it can feel so unfair. Your friend can do the same things you do and be fine. You do one thing “wrong” and suddenly you’re waking up at 2 AM with that familiar burning. That doesn’t mean you’re dirty. It doesn’t mean you failed. It may mean your bladder’s natural defense needs support. And here’s the second part: Bacteria are not helpless. Some bacteria are tougher than others. Some learn how to survive the same tools we keep using. That’s why the antibiotic that worked the first time may not feel as reliable after the fifth, sixth, or seventh round. So the real issue is not just “how do we numb the pain?” It’s not just “how do we block sticking?” It’s not even just “how do we clear what’s there right now?” The deeper question is: How do we help the bladder become stronger between flare-ups, so every little scare does not have to turn into another emergency? That was the sentence that changed everything for me. Because Claire’s problem wasn’t compliance. My problem wasn’t compliance. Thousands of women’s problem isn’t compliance. The problem is that most UTI products are built for the wrong job. AZO can numb the burning, but it does not support the bladder’s natural defense. And it can turn your pee orange. Sometimes neon orange. Sometimes “I just stained the toilet at urgent care” orange. D-Mannose can help bind certain bacteria, but it does not strengthen the bladder lining. Cranberry can help reduce sticking, but it does not rebuild the bladder’s natural shield. Probiotics can support general balance, but they are not a direct bladder defense. Antibiotics can be important when you have an active infection. I still use them when they are needed. But antibiotics are not a daily plan for women who are tired of every flare-up becoming an emergency. They are for when things get bad. But Claire didn’t want to keep getting there. Neither did I. So Dr. Santos showed me the actual approach I had been missing. It involved three things happening together: 1. A daily bladder defense — support that helps make the bladder a harder place for unwanted bacteria to thrive. 2. Resistance-aware support — a mechanism that does not depend on bacteria being weak, new, or easy. 3. Bladder lining support — helping the bladder’s natural inner shield do the job it was supposed to do all along. That is when she brought up two compounds I had been ignoring for years: Carvacrol from oregano oil. And thymoquinone from black seed oil. Not random “herbal wellness” fluff. Not a cheap oregano capsule from a health store. Not cranberry with a prettier label. Carvacrol is the active compound in oregano oil. In simple terms? It helps support a bladder environment that is tougher for unwanted bacteria. Thymoquinone is the main active compound in black seed oil. And it supports the bladder’s natural protective lining — the layer that helps keep bacteria from sticking in the first place. Together, the idea was simple: Instead of waiting until the burning starts... Instead of waiting until the urgency ruins your day... Instead of waiting until you need another emergency plan... You support the bladder every day. The bladder environment becomes harder for unwanted bacteria to thrive in. And the bladder lining gets support so it is less exposed next time. Not another orange-pee pain pill. Not another “just wait for the antibiotics to kick in.” Not another emergency-only patch. A daily bladder defense. And here’s the part that made my blood boil: The women’s health industry knows women are tired. We know they are keeping supplies in their cabinet, purse, and travel bag. We know they are sitting in meetings while silently counting the minutes until they can pee again. We know they are scared when they feel that first little sting. We know some women are planning their whole day around the nearest bathroom. But what do we keep handing them? A pain dye that stains everything. A cranberry bottle that blocks but doesn’t strengthen. D-Mannose that may help some women but does not solve the full problem. Another antibiotic. Another “come back if it happens again.” See how that works? The system is designed to manage the next flare-up. Not help women stop living in fear of the next one. Now here’s the problem I ran into... Most oregano supplements are garbage. I tried a cheap oregano capsule. Low potency. No clear carvacrol amount. Smelled awful. Tasted worse. Gave me oregano burps. Did nothing for my bladder confidence. I tried a “urinary health” probiotic. Nice bottle. Soft marketing. No direct bladder defense support. I tried cranberry again. I tried D-Mannose again. I tried the same things I had told patients to try for years. And I kept thinking: If this worked so well, why are so many women still getting UTIs back to back? Because here’s the thing: A generic cranberry capsule is NOT the same as a true daily bladder defense. And a weak oregano capsule is NOT the same as a high-potency oregano oil softgel built for women who are tired of the UTI treadmill. Most supplements fail at one of the three requirements. Too weak. Wrong target. Bad format. Hard to take every day. Orange pee. Bad taste. Mess. Stomach issues. Or they only help when you are already miserable. Until I found Orynwell. They had an Oregano + Black Seed Oil softgel. Not a generic multivitamin. Not a low-dose oregano powder. Not a cranberry pill pretending to be a breakthrough. A dual-action bladder defense formula. With the two compounds I was looking for: High-potency oregano oil standardized for Carvacrol. Black seed oil with Thymoquinone. And the format mattered. Two softgels a day with food. No orange pee. No bad taste. No drops under your tongue. No staining. No “ugh, I have to take that thing.” Just two softgels with breakfast. Thirty seconds. Done. When I dug into the formulation? It made sense. Orynwell delivers 6,000mg of high-potency oregano oil equivalent from a 20:1 extract, with 165mg of Carvacrol per serving. It also includes 200mg of black seed oil. That means it is built around the two things recurrent sufferers actually need: Support a bladder environment that is harder for unwanted bacteria to thrive in. Support the protective lining bacteria try to stick to. They weren’t just selling “urinary health.” They understood what most products miss. They knew why women keep saying: “I did everything right and it still came back.” They knew why so many women are tired of being told: “Some people are just prone to them.” They knew why “just drink more water” feels insulting when your life is already shrinking around your bladder. And here’s where I had to face what I had done to my patients. When Claire was filling antibiotic prescriptions from me? Money every month. Plus the D-Mannose. Plus the probiotics. Plus my office visits every 6-8 weeks. Plus the urgent care trips when symptoms hit on weekends. Plus the cranberry supplements. Plus the OTC AZO she kept buying every time the burning came back. She was spending thousands of dollars a year. Every single year. Just to manage a cycle that kept coming back. The Orynwell softgels? A fraction of what she had been spending on things that only helped part of the problem. Designed to support the bladder before the next flare-up takes over her life. Carvacrol to help support a tougher bladder environment for unwanted bacteria. Thymoquinone to support the bladder’s natural protective lining. Two softgels with breakfast. No orange pee. No staining. No “keep wearing dark underwear just in case.” I started using them myself first. Week 2: The constant low-level urgency — that background pressure I had stopped noticing because it had become my normal — began to quiet down. Not overnight. Not like a pain pill. More like my bladder stopped yelling at me all day. Week 4: I reached the point in my cycle where I would normally start worrying. That little voice in my head would usually start: Is this the day? Is that the first sting? Should I call in a prescription now? But nothing started. I didn’t trust it yet. But I noticed I had not checked the bathroom location once that morning. Something I had not done in fourteen months. Week 8: I went to a conference — full day, back-to-back sessions — and did not calculate bathroom access once. No silent panic. No sitting near the aisle “just in case.” No prescription in my purse feeling like a life raft. The gap between my last scare and that morning was already longer than any gap I had had in over a year. Week 12: Full assessment. The urgency was gone. The dread was gone. I wore light-colored pants to work for the first time since this started. That sounds small unless you’ve lived it. But if you’ve ever avoided white pants because you were scared of orange pee, leaks, stains, or sudden urgency... You know exactly what that meant. Then I called Claire. And every other patient I had failed. “I need to tell you something. I was treating your bladder like it only needed emergency help after the burning started. But for recurring sufferers, the bladder needs daily support before the next flare-up takes over. I didn’t understand the difference. But I do now.” Claire, Week 6: “Dr. Harlan, I just hit six weeks without a scare. That hasn’t happened in three years. And for the first time since this started, I didn’t check where the bathroom was before I sat down at a restaurant. I didn’t even think about it until I realized I wasn’t thinking about it.” Before: Bladder scares every few weeks. Multiple antibiotic courses. Cranberry. D-Mannose. AZO. Doctor visits. Bathroom mapping. Purse full of backup products. After 6 weeks: No new flare-up. No emergency trip. No orange pee. No checking the restaurant bathroom before ordering food. The gap that had been collapsing for years finally held. She drove four hours to her college roommate’s birthday weekend last month. First overnight trip in two years. No backup plan. No pharmacy location mapped. No calculating whether she was too far from home. She called me from the road on the way back. “I didn’t think about my bladder once the entire weekend. Not once.” That was the moment I knew. She did not just get symptom relief. She got mental relief. She booked a trip to Europe with her sister for next spring. Something she had said no to three years in a row. She got her life back. This is the daily bladder defense most women have never been told about. Because the moment your bladder feels more supported, everything changes. You stop treating every tiny sting like a full emergency. You stop keeping three different products in your purse. You stop wondering if one normal day is about to turn into another ruined week. You stop asking: “What did I do wrong this time?” Because maybe you didn’t do anything wrong. Maybe your bladder just needed better defense. Now here’s what I need you to understand about timing: The urgency is real. Your bladder does not wait until you are ready. One small scare becomes a weekend ruined. One weekend becomes another doctor visit. Another doctor visit becomes another prescription. Another prescription becomes another month of wondering what it is doing to your gut, your yeast balance, and your long-term resistance. And the fear builds. If you are at one or two UTIs a year right now — this is the time to start supporting your bladder before the pattern gets worse. If you are already dealing with symptoms every few weeks — you already know how fast one normal morning can turn into “I need to find a bathroom right now.” If you are reading this and the gap between scares is measured in weeks, not months — act now. Because this cycle does not just hurt. It shrinks your life. It makes you say no to trips. No to long car rides. No to sex. No to light-colored pants. No to sitting through a movie. No to sleeping through the night. No to feeling normal in your own body. And if you are someone who has been dealing with this — burning, pressure, constant urge to go, the dread, the calculating, the bathroom mapping — and nothing has worked? It is not because you are dirty. It is not because you did not drink enough water. It is not because you forgot to pee after sex one time. It is not because you failed. It may be because you have only been given products that deal with the problem after it starts. Pain relief after the burn. Cranberry after the worry. D-Mannose after the scare. Antibiotics after things get bad. But your bladder may need daily defense before the next flare-up starts. And that is exactly what Orynwell was built to support. Orynwell has a 90-day money-back guarantee — if you don’t feel the difference, you’re not out anything. And honestly? Even if you are skeptical, try it for 90 days. Take two softgels with breakfast. Watch what happens to the gap between scares. Watch whether that background urgency starts to quiet. Watch whether you stop checking for bathrooms without even realizing it. Watch whether your purse stops feeling like an emergency kit. That is your proof. Because the UTI industry is not coming to save you. There is too much money in the cycle: The urgent care visit. The antibiotic. The AZO. The cranberry. The D-Mannose. The probiotic. The refill. The next scare. The next appointment. A 63-year-old bladder researcher taught me more in 20 minutes than I learned in nearly three decades of OB-GYN training. It is about time I passed that lesson on. Learn More → https://orynwell.com/pages/uti-cycle-reset-report-305 P.S. — I still tell women to see a doctor when they have active UTI symptoms. Orynwell is not an emergency antibiotic replacement. It is a daily bladder support routine for women who are tired of waiting for the next flare-up to take over their life. P.P.S. — If your UTIs keep coming back, stop spending all your energy on products that only step in after you are already suffering. Every flare-up still leaves you with the same pain, the same fear, and the same emergency cycle. A stronger daily bladder defense is the part most women were never told to focus on. P.P.P.S. — Claire: “Five years. Bladder scares every few weeks. Thousands of dollars on antibiotics, cranberry, D-Mannose, AZO, and doctor visits. I did everything right and it still came back. Two softgels with breakfast finally gave me a daily defense I could actually live with. No orange pee. No taste. No constant fear. Don’t wait like I did.”

UTI Cycle Reset
UTI Cycle Reset
+1
Inactive2 days
orynwell.com
Build A Bladder Bacteria Don’t Want
Learn more

I've been an OB-GYN for 27 years. And if your UTIs keep coming back faster every cycle, your antibiotics seem to give you less peace each time, and everything you try only helps after you’re already miserable... I’m about to tell you why the usual UTI advice may be missing the real problem. And by the end of this, you're gonna be pissed. My name is Dr. Sarah Harlan. Board-certified OB-GYN and women’s urinary health specialist. Twenty-seven years helping women with chronic urinary discomfort, bladder infections, and recurring UTI patterns. Over 9,800 patients. And I’m breaking ranks with my own profession to tell you this. Because there are two things happening right now: One — Most UTI products only step in after you are already uncomfortable. After the burning starts. After the urgency takes over. After you are already checking bathrooms, cancelling plans, and wondering if this is about to become another full-blown bladder scare. AZO can help numb the burning. Cranberry and D-Mannose try to help once bacteria are already part of the problem. Antibiotics may be needed when things get bad. But none of these are built as a gentle daily way to support your bladder’s own defense before the next flare-up takes over your life. Two — The UTI industry makes money every time your bladder scare turns into another emergency. Another appointment. Another prescription. Another orange-pee pain pill. Another “keep this in your purse just in case.” So the system keeps you managing the next flare-up. Not supporting your bladder before the next one begins. So let me tell you what happened with one of my patients, because her story is going to open your eyes to how messed up this really is. Her name was Claire. 48 years old. For YEARS, and I mean like five straight years, she was dealing with this. Her infections? It started with one UTI in the spring. A straightforward case. Burning, urgency, frequency. She came to me early — week two. I told her we’d handle it. No big deal. I prescribed trimethoprim-sulfamethoxazole. Standard first-line antibiotic. “Take the full course,” I said. “Be consistent.” She was consistent. She took every single pill at the exact same time every morning for seven days. Religiously. Never missed a dose. And you know what happened? The infection didn’t stay gone. Six weeks later, the same burning. The same urgency. The same pressure building in her lower belly that told her she had maybe twenty minutes before it became unbearable. And then it accelerated. The second course seemed to hold for five weeks. The third for four. By the end of year two, she was getting a new bladder scare every three weeks — sometimes before she had even stopped worrying about the last one. Each round gave her less peace than the last. She stopped booking overnight trips. Stopped committing to anything more than an hour from home. Started mapping bathroom locations before she went anywhere — restaurants, malls, her daughter’s school events. She told me once: “I plan my entire life around where the nearest bathroom is.” And the fear? It wasn’t just inconvenience anymore. She was terrified it would keep happening. She had noticed the gap between infections shrinking again and she was panicking. She had a 9-year-old daughter who had started noticing that “Mommy always has to leave early” — and Claire would change the subject and hold back tears, scared this was just her life now. And here’s what makes me sick to my stomach: I was the doctor she trusted. Multiple visits. Year after year. Thousands of dollars in appointments, prescriptions, antibiotic rotations, specialist referrals... the whole nine yards. And you know what I kept telling her? “The antibiotic needs more time.” “Try switching to nitrofurantoin.” “It’s manageable. We just need to find the right combination.” “Be more consistent with hydration.” BE MORE CONSISTENT. This woman was doing everything right. She was taking every antibiotic course to completion. She was drinking water. She was peeing after sex. She was wiping the right way. She was avoiding bubble baths. She had cranberry in her cabinet, D-Mannose in her kitchen, AZO in her purse, and a backup prescription in her travel bag. And I was still making her feel like she wasn’t doing enough. But here’s where it gets worse — and this is the part that haunts me now. I switched her to a different antibiotic. Then another. Then I added a low-dose daily suppressive antibiotic. Then D-Mannose powder. Then a probiotic protocol. Then cranberry extract. Then I suggested AZO every time she felt symptoms coming on. Then a urologist referral for cystoscopy. You know what happened? The bladder scares kept coming back. The suppressive antibiotic gave her a few quiet months — then the symptoms came back the moment she stopped. The D-Mannose helped a little at first, then did nothing. The probiotics “helped a little with digestion” but didn’t change the UTI pattern. The cranberry extract was “like taking sugar pills at this point.” The AZO turned her urine orange and masked the burning for a few hours. And the urologist? After the cystoscopy found nothing structurally wrong, he told her: “Some women are just prone to recurrent infections.” I watched this woman — who did everything I told her, spent thousands of dollars, followed every protocol — get worse. Not better. Worse. And I didn’t understand why. Until a 63-year-old bladder researcher taught me more about recurring UTIs in 20 minutes than I learned in nearly three decades of OB-GYN training. October 2024. San Francisco. American College of Obstetricians and Gynecologists Annual Meeting. I was calculating in my head whether I had time to use the bathroom again before the next session. Because at 54, my own UTI cycle had started fourteen months earlier. And nothing I had been prescribing to patients for 27 years was giving me peace either. Worse — the fear was getting stronger every cycle. The gap that had started at eight weeks was now down to three. I had a prescription in my purse at all times. I knew every bathroom in every conference center I had visited that year. That’s when I saw her. Dr. Evelyn Santos. 63 years old. Presenting for two hours straight. No distraction. No urgency. No quiet slipping out mid-session to find a bathroom. Moving through the day the way a person moves when she is not calculating distances and timing with every step. She had mentioned in her presentation that she had dealt with chronic recurring UTIs herself for years and finally changed her approach. I had to know how. I walked over. “Excuse me — I’m an OB-GYN. I’ve been dealing with recurrent UTIs for fourteen months. The gap between infections feels like it’s getting shorter. I’ve tried everything I prescribe to patients. Nothing is breaking the cycle.” She smiled. The kind of smile that knows something you don’t. Then she asked me one question: “Dr. Harlan, are you still waiting until the burning starts before you support the bladder?” I froze. Because that was exactly what I had been doing. AZO after the burning started. Cranberry after the worry came back. D-Mannose after she felt that first familiar pressure. Another antibiotic after things got bad. Every solution I gave her was reacting to the flare-up. But none of it was helping her bladder build the daily defense it needed between scares. She looked at me and said: “That’s the trap. You keep treating every flare-up after it starts. But for recurrent sufferers, the bladder needs support before the next one begins.” My stomach dropped. Then she said something I will never forget: “You’re fighting every spark after the smoke alarm goes off. But you’re not making the room harder to burn.” She gestured to an empty table. “May I show you something? It will take twenty minutes. But it will change how you understand this completely.” What she taught me in 20 minutes changed everything. She drew a simple diagram on a napkin. “Your treatment model treats every UTI like a separate event. So you clear the active infection. You tell her to drink water. You tell her to pee after sex. You give her cranberry. You give her AZO.” She tapped the napkin. “But look at the pattern. The same woman keeps getting hit again and again. The same pain. The same fear. The same emergency cycle.” The bladder. Then she drew a circle around it. “Most products are focused on what happens after the problem has already started.” Pain relief after the burning starts. Cranberry after the fear comes back. D-Mannose after the first pressure hits. Antibiotics after things get bad. Then she wrote two words inside the circle: DAILY DEFENSE. “That’s the part most UTI products ignore.” Now pause for a second. You know what’s insane? We learned in medical school that the bladder has a natural protective lining. We learned that bacteria need to stick, survive, and grow before a UTI takes hold. We learned that some bacteria become harder to deal with after repeated exposure to antibiotics. We learned that recurrent UTI sufferers are not always doing something wrong. We know this. And yet we keep giving women the same advice: Drink more water. Pee after sex. Try cranberry. Take AZO. Take another antibiotic. Come back if it happens again. And when it does happen again? We repeat the same loop. Again. And again. And again. Here’s what’s actually happening underneath: Your bladder is supposed to have a natural inner lining. Think of it like a slick protective shield. When that shield is strong, bacteria have a harder time sticking to the bladder wall. They have a harder time settling in. They have a harder time turning one bad day into another full-blown scare. But in a lot of women with recurring UTIs, that lining can become worn down. That means the same small amount of bacteria that another woman’s body shrugs off can become a problem for you. That’s why it can feel so unfair. Your friend can do the same things you do and be fine. You do one thing “wrong” and suddenly you’re waking up at 2 AM with that familiar burning. That doesn’t mean you’re dirty. It doesn’t mean you failed. It may mean your bladder’s natural defense needs support. And here’s the second part: Bacteria are not helpless. Some bacteria are tougher than others. Some learn how to survive the same tools we keep using. That’s why the antibiotic that worked the first time may not feel as reliable after the fifth, sixth, or seventh round. So the real issue is not just “how do we numb the pain?” It’s not just “how do we block sticking?” It’s not even just “how do we clear what’s there right now?” The deeper question is: How do we help the bladder become stronger between flare-ups, so every little scare does not have to turn into another emergency? That was the sentence that changed everything for me. Because Claire’s problem wasn’t compliance. My problem wasn’t compliance. Thousands of women’s problem isn’t compliance. The problem is that most UTI products are built for the wrong job. AZO can numb the burning, but it does not support the bladder’s natural defense. And it can turn your pee orange. Sometimes neon orange. Sometimes “I just stained the toilet at urgent care” orange. D-Mannose can help bind certain bacteria, but it does not strengthen the bladder lining. Cranberry can help reduce sticking, but it does not rebuild the bladder’s natural shield. Probiotics can support general balance, but they are not a direct bladder defense. Antibiotics can be important when you have an active infection. I still use them when they are needed. But antibiotics are not a daily plan for women who are tired of every flare-up becoming an emergency. They are for when things get bad. But Claire didn’t want to keep getting there. Neither did I. So Dr. Santos showed me the actual approach I had been missing. It involved three things happening together: 1. A daily bladder defense — support that helps make the bladder a harder place for unwanted bacteria to thrive. 2. Resistance-aware support — a mechanism that does not depend on bacteria being weak, new, or easy. 3. Bladder lining support — helping the bladder’s natural inner shield do the job it was supposed to do all along. That is when she brought up two compounds I had been ignoring for years: Carvacrol from oregano oil. And thymoquinone from black seed oil. Not random “herbal wellness” fluff. Not a cheap oregano capsule from a health store. Not cranberry with a prettier label. Carvacrol is the active compound in oregano oil. In simple terms? It helps support a bladder environment that is tougher for unwanted bacteria. Thymoquinone is the main active compound in black seed oil. And it supports the bladder’s natural protective lining — the layer that helps keep bacteria from sticking in the first place. Together, the idea was simple: Instead of waiting until the burning starts... Instead of waiting until the urgency ruins your day... Instead of waiting until you need another emergency plan... You support the bladder every day. The bladder environment becomes harder for unwanted bacteria to thrive in. And the bladder lining gets support so it is less exposed next time. Not another orange-pee pain pill. Not another “just wait for the antibiotics to kick in.” Not another emergency-only patch. A daily bladder defense. And here’s the part that made my blood boil: The women’s health industry knows women are tired. We know they are keeping supplies in their cabinet, purse, and travel bag. We know they are sitting in meetings while silently counting the minutes until they can pee again. We know they are scared when they feel that first little sting. We know some women are planning their whole day around the nearest bathroom. But what do we keep handing them? A pain dye that stains everything. A cranberry bottle that blocks but doesn’t strengthen. D-Mannose that may help some women but does not solve the full problem. Another antibiotic. Another “come back if it happens again.” See how that works? The system is designed to manage the next flare-up. Not help women stop living in fear of the next one. Now here’s the problem I ran into... Most oregano supplements are garbage. I tried a cheap oregano capsule. Low potency. No clear carvacrol amount. Smelled awful. Tasted worse. Gave me oregano burps. Did nothing for my bladder confidence. I tried a “urinary health” probiotic. Nice bottle. Soft marketing. No direct bladder defense support. I tried cranberry again. I tried D-Mannose again. I tried the same things I had told patients to try for years. And I kept thinking: If this worked so well, why are so many women still getting UTIs back to back? Because here’s the thing: A generic cranberry capsule is NOT the same as a true daily bladder defense. And a weak oregano capsule is NOT the same as a high-potency oregano oil softgel built for women who are tired of the UTI treadmill. Most supplements fail at one of the three requirements. Too weak. Wrong target. Bad format. Hard to take every day. Orange pee. Bad taste. Mess. Stomach issues. Or they only help when you are already miserable. Until I found Orynwell. They had an Oregano + Black Seed Oil softgel. Not a generic multivitamin. Not a low-dose oregano powder. Not a cranberry pill pretending to be a breakthrough. A dual-action bladder defense formula. With the two compounds I was looking for: High-potency oregano oil standardized for Carvacrol. Black seed oil with Thymoquinone. And the format mattered. Two softgels a day with food. No orange pee. No bad taste. No drops under your tongue. No staining. No “ugh, I have to take that thing.” Just two softgels with breakfast. Thirty seconds. Done. When I dug into the formulation? It made sense. Orynwell delivers 6,000mg of high-potency oregano oil equivalent from a 20:1 extract, with 165mg of Carvacrol per serving. It also includes 200mg of black seed oil. That means it is built around the two things recurrent sufferers actually need: Support a bladder environment that is harder for unwanted bacteria to thrive in. Support the protective lining bacteria try to stick to. They weren’t just selling “urinary health.” They understood what most products miss. They knew why women keep saying: “I did everything right and it still came back.” They knew why so many women are tired of being told: “Some people are just prone to them.” They knew why “just drink more water” feels insulting when your life is already shrinking around your bladder. And here’s where I had to face what I had done to my patients. When Claire was filling antibiotic prescriptions from me? Money every month. Plus the D-Mannose. Plus the probiotics. Plus my office visits every 6-8 weeks. Plus the urgent care trips when symptoms hit on weekends. Plus the cranberry supplements. Plus the OTC AZO she kept buying every time the burning came back. She was spending thousands of dollars a year. Every single year. Just to manage a cycle that kept coming back. The Orynwell softgels? A fraction of what she had been spending on things that only helped part of the problem. Designed to support the bladder before the next flare-up takes over her life. Carvacrol to help support a tougher bladder environment for unwanted bacteria. Thymoquinone to support the bladder’s natural protective lining. Two softgels with breakfast. No orange pee. No staining. No “keep wearing dark underwear just in case.” I started using them myself first. Week 2: The constant low-level urgency — that background pressure I had stopped noticing because it had become my normal — began to quiet down. Not overnight. Not like a pain pill. More like my bladder stopped yelling at me all day. Week 4: I reached the point in my cycle where I would normally start worrying. That little voice in my head would usually start: Is this the day? Is that the first sting? Should I call in a prescription now? But nothing started. I didn’t trust it yet. But I noticed I had not checked the bathroom location once that morning. Something I had not done in fourteen months. Week 8: I went to a conference — full day, back-to-back sessions — and did not calculate bathroom access once. No silent panic. No sitting near the aisle “just in case.” No prescription in my purse feeling like a life raft. The gap between my last scare and that morning was already longer than any gap I had had in over a year. Week 12: Full assessment. The urgency was gone. The dread was gone. I wore light-colored pants to work for the first time since this started. That sounds small unless you’ve lived it. But if you’ve ever avoided white pants because you were scared of orange pee, leaks, stains, or sudden urgency... You know exactly what that meant. Then I called Claire. And every other patient I had failed. “I need to tell you something. I was treating your bladder like it only needed emergency help after the burning started. But for recurring sufferers, the bladder needs daily support before the next flare-up takes over. I didn’t understand the difference. But I do now.” Claire, Week 6: “Dr. Harlan, I just hit six weeks without a scare. That hasn’t happened in three years. And for the first time since this started, I didn’t check where the bathroom was before I sat down at a restaurant. I didn’t even think about it until I realized I wasn’t thinking about it.” Before: Bladder scares every few weeks. Multiple antibiotic courses. Cranberry. D-Mannose. AZO. Doctor visits. Bathroom mapping. Purse full of backup products. After 6 weeks: No new flare-up. No emergency trip. No orange pee. No checking the restaurant bathroom before ordering food. The gap that had been collapsing for years finally held. She drove four hours to her college roommate’s birthday weekend last month. First overnight trip in two years. No backup plan. No pharmacy location mapped. No calculating whether she was too far from home. She called me from the road on the way back. “I didn’t think about my bladder once the entire weekend. Not once.” That was the moment I knew. She did not just get symptom relief. She got mental relief. She booked a trip to Europe with her sister for next spring. Something she had said no to three years in a row. She got her life back. This is the daily bladder defense most women have never been told about. Because the moment your bladder feels more supported, everything changes. You stop treating every tiny sting like a full emergency. You stop keeping three different products in your purse. You stop wondering if one normal day is about to turn into another ruined week. You stop asking: “What did I do wrong this time?” Because maybe you didn’t do anything wrong. Maybe your bladder just needed better defense. Now here’s what I need you to understand about timing: The urgency is real. Your bladder does not wait until you are ready. One small scare becomes a weekend ruined. One weekend becomes another doctor visit. Another doctor visit becomes another prescription. Another prescription becomes another month of wondering what it is doing to your gut, your yeast balance, and your long-term resistance. And the fear builds. If you are at one or two UTIs a year right now — this is the time to start supporting your bladder before the pattern gets worse. If you are already dealing with symptoms every few weeks — you already know how fast one normal morning can turn into “I need to find a bathroom right now.” If you are reading this and the gap between scares is measured in weeks, not months — act now. Because this cycle does not just hurt. It shrinks your life. It makes you say no to trips. No to long car rides. No to sex. No to light-colored pants. No to sitting through a movie. No to sleeping through the night. No to feeling normal in your own body. And if you are someone who has been dealing with this — burning, pressure, constant urge to go, the dread, the calculating, the bathroom mapping — and nothing has worked? It is not because you are dirty. It is not because you did not drink enough water. It is not because you forgot to pee after sex one time. It is not because you failed. It may be because you have only been given products that deal with the problem after it starts. Pain relief after the burn. Cranberry after the worry. D-Mannose after the scare. Antibiotics after things get bad. But your bladder may need daily defense before the next flare-up starts. And that is exactly what Orynwell was built to support. Orynwell has a 90-day money-back guarantee — if you don’t feel the difference, you’re not out anything. And honestly? Even if you are skeptical, try it for 90 days. Take two softgels with breakfast. Watch what happens to the gap between scares. Watch whether that background urgency starts to quiet. Watch whether you stop checking for bathrooms without even realizing it. Watch whether your purse stops feeling like an emergency kit. That is your proof. Because the UTI industry is not coming to save you. There is too much money in the cycle: The urgent care visit. The antibiotic. The AZO. The cranberry. The D-Mannose. The probiotic. The refill. The next scare. The next appointment. A 63-year-old bladder researcher taught me more in 20 minutes than I learned in nearly three decades of OB-GYN training. It is about time I passed that lesson on. Learn More → https://orynwell.com/pages/uti-cycle-reset-report-305 P.S. — I still tell women to see a doctor when they have active UTI symptoms. Orynwell is not an emergency antibiotic replacement. It is a daily bladder support routine for women who are tired of waiting for the next flare-up to take over their life. P.P.S. — If your UTIs keep coming back, stop spending all your energy on products that only step in after you are already suffering. Every flare-up still leaves you with the same pain, the same fear, and the same emergency cycle. A stronger daily bladder defense is the part most women were never told to focus on. P.P.P.S. — Claire: “Five years. Bladder scares every few weeks. Thousands of dollars on antibiotics, cranberry, D-Mannose, AZO, and doctor visits. I did everything right and it still came back. Two softgels with breakfast finally gave me a daily defense I could actually live with. No orange pee. No taste. No constant fear. Don’t wait like I did.”

UTI Cycle Reset
UTI Cycle Reset
+1
Inactive1 day
orynwell.com
Build A Bladder Bacteria Don’t Want
Learn more

I've been an OB-GYN for 27 years. And if your UTIs keep showing up after sex, your antibiotics seem to give you less peace every cycle, and your doctor keeps telling you to “just pee after sex” or “try a stronger prescription”... I’m about to tell you why the usual post-sex UTI advice may be missing the real problem. And by the end of this, you're gonna be pissed. My name is Dr. Sarah Harlan. Board-certified OB-GYN and women’s urinary health specialist. Twenty-seven years helping women with chronic urinary discomfort, bladder infections, and recurring UTI patterns. Over 9,800 patients. And I’m breaking ranks with my own profession to tell you this. Because there are three things happening right now: One — Most women are told to obsess over what caused the UTI after intimacy. Sex. Partner hygiene. Not peeing fast enough. Wiping. Tight jeans. Dehydration. Bad luck. But once the bacteria reach your bladder, the real question is simple: Can they survive there? Two — Most UTI products were never built to answer that question. AZO masks the burning. Cranberry and D-Mannose try to stop bacteria from sticking. Antibiotics may be needed when things get bad, but they are not built as a gentle daily bladder defense. Three — The UTI industry makes money every time one intimate night turns into another bladder emergency. Another appointment. Another prescription. Another orange-pee pain pill. Another “keep this in your purse just in case.” So let me tell you what happened with one of my patients, because her story is going to open your eyes to how messed up this really is. Her name was Claire. 48 years old. For YEARS, and I mean like five straight years, she was dealing with this. Her infections? They almost always seemed to show up after sex. At first, it was one UTI after a normal weekend with her husband. A straightforward case. Burning, urgency, frequency. She came to me early — week two. I told her we’d handle it. No big deal. I prescribed trimethoprim-sulfamethoxazole. Standard first-line antibiotic. “Take the full course,” I said. “Be consistent.” She was consistent. She took every single pill at the exact same time every morning for seven days. Religiously. Never missed a dose. And you know what happened? The infection didn’t stay gone. Six weeks later, after another intimate night, the same burning. The same urgency. The same pressure building in her lower belly that told her she had maybe twenty minutes before it became unbearable. And then it accelerated. The second course seemed to hold for five weeks. The third for four. By the end of year two, she was getting a new bladder scare every three weeks — usually right after she had finally started feeling normal again with her husband. Each round gave her less peace than the last. She stopped booking overnight trips. Stopped committing to anything more than an hour from home. Started mapping bathroom locations before she went anywhere — restaurants, malls, her daughter’s school events. She told me once: “I plan my entire life around where the nearest bathroom is.” And the fear? It wasn’t just inconvenience anymore. She was terrified of intimacy. Not because she didn’t love her husband. But because every normal night together felt like the start of a countdown. She had a 9-year-old daughter who had started noticing that “Mommy always has to leave early” — and Claire would change the subject and hold back tears, scared this was just her life now. And here’s what makes me sick to my stomach: I was the doctor she trusted. Multiple visits. Year after year. Thousands of dollars in appointments, prescriptions, antibiotic rotations, specialist referrals... the whole nine yards. And you know what I kept telling her? “The antibiotic needs more time.” “Try switching to nitrofurantoin.” “It’s manageable. We just need to find the right combination.” “Be more consistent with hydration.” “Make sure you pee after sex.” BE MORE CONSISTENT. This woman was doing everything right. She was taking every antibiotic course to completion. She was drinking water. She was peeing after sex. She was wiping the right way. She was avoiding bubble baths. She had cranberry in her cabinet, D-Mannose in her kitchen, AZO in her purse, and a backup prescription in her travel bag. And I was still making her feel like she wasn’t doing enough. But here’s where it gets worse — and this is the part that haunts me now. I switched her to a different antibiotic. Then another. Then I added a low-dose daily suppressive antibiotic. Then D-Mannose powder. Then a probiotic protocol. Then cranberry extract. Then AZO every time she felt symptoms coming on. Then a urologist referral for cystoscopy. You know what happened? The bladder scares kept coming back. The suppressive antibiotic gave her a few quiet months — then the symptoms came back the moment she stopped. The D-Mannose helped a little at first, then did nothing. The probiotics “helped a little with digestion” but didn’t change the UTI pattern. The cranberry extract was “like taking sugar pills at this point.” The AZO turned her urine orange and masked the burning for a few hours. And the urologist? After the cystoscopy found nothing structurally wrong, he told her: “Some women are just prone to recurrent infections.” I watched this woman — who did everything I told her, spent thousands of dollars, followed every protocol — get worse. Not better. Worse. And I didn’t understand why. Until a 63-year-old bladder researcher taught me more about recurring UTIs in 20 minutes than I learned in nearly three decades of OB-GYN training. October 2024. San Francisco. American College of Obstetricians and Gynecologists Annual Meeting. I was calculating in my head whether I had time to use the bathroom again before the next session. Because at 54, my own post-intimacy UTI cycle had started fourteen months earlier. And nothing I had been prescribing to patients for 27 years was giving me peace either. Worse — the fear was getting stronger every cycle. The gap that had started at eight weeks was now down to three. I had a prescription in my purse at all times. I knew every bathroom in every conference center I had visited that year. And I had started doing something I hated admitting. I had started avoiding intimacy too. Not because I wanted to. Because I was scared of what might happen the next morning. That’s when I saw her. Dr. Evelyn Santos. 63 years old. Presenting for two hours straight. No distraction. No urgency. No quiet slipping out mid-session to find a bathroom. Moving through the day the way a person moves when she is not calculating distances and timing with every step. She had mentioned in her presentation that she had dealt with chronic recurring UTIs herself for years and finally changed her approach. I had to know how. I walked over. “Excuse me — I’m an OB-GYN. I’ve been dealing with recurrent UTIs for fourteen months. They often seem to happen after sex. The gap between scares feels like it’s getting shorter. I’ve tried everything I prescribe to patients. Nothing is breaking the cycle.” She smiled. The kind of smile that knows something you don’t. Then she asked me one question: “Dr. Harlan, are you still thinking about this as a ‘what caused it after sex’ problem?” I froze. Because that was exactly how I had been thinking about it. Sex. Partner hygiene. Not peeing fast enough after sex. Not enough water. Tight clothes. Bad luck. She looked at me and said: “That’s the trap. You can spend years trying to figure out how bacteria got in. But once they reach the bladder, the real question is: why are they surviving there?” My stomach dropped. Then she said something I will never forget: “You’re treating every flare-up like a new accident. But in many recurrent sufferers, the bladder has become too easy for bacteria to survive in.” She looked at me steadily. “The problem isn’t that your patient is dirty. It isn’t that she didn’t try hard enough. It’s that her bladder environment is not defended the way it should be.” Then she said: “You’re fighting every spark after the smoke alarm goes off. But you’re not making the room harder to burn.” She gestured to an empty table. “May I show you something? It will take twenty minutes. But it will change how you understand this completely.” What she taught me in 20 minutes changed everything. She drew a simple diagram on a napkin. “Your treatment model treats every UTI like a separate event. So you clear the active infection. You tell her to drink water. You tell her to pee after sex. You give her cranberry to block sticking. You give her AZO to numb the burning.” She tapped the napkin. “But look at the pattern. The same woman keeps getting hit again and again. Different triggers. Same final destination.” The bladder. Then she drew a circle around it. “It doesn’t matter if the bacteria came from sex, partner hygiene, wiping, water exposure, underwear, or bad luck. Once they reach the bladder, they all end up in the same place.” Then she drew two words inside the circle: SURVIVE HERE. “That’s the part most UTI products ignore.” Now pause for a second. You know what’s insane? We learned in medical school that the bladder has a natural protective lining. We learned that bacteria need to stick, survive, and grow before a UTI takes hold. We learned that some bacteria become harder to deal with after repeated exposure to antibiotics. We learned that recurrent UTI sufferers are not always doing something wrong. We know this. And yet we keep giving women the same advice: Drink more water. Pee after sex. Try cranberry. Take AZO. Take another antibiotic. Come back if it happens again. And when it does happen again? We repeat the same loop. Again. And again. And again. Here’s what’s actually happening underneath: Your bladder is supposed to have a natural inner lining. Think of it like a slick protective shield. When that shield is strong, bacteria have a harder time sticking to the bladder wall. They have a harder time settling in. They have a harder time turning one exposure into another full-blown scare. But in a lot of women with recurring UTIs, that lining can become worn down. That means the same small amount of bacteria that another woman’s body shrugs off can become a problem for you. That’s why it can feel so unfair. Your friend can forget to pee after sex and be fine. You do everything right and still wake up with that familiar burn. That doesn’t mean you’re dirty. It doesn’t mean you failed. It may mean your bladder’s natural shield needs support. And here’s the second part: Bacteria are not helpless. Some bacteria are tougher than others. Some learn how to survive the same tools we keep using. That’s why the antibiotic that worked the first time may not feel as reliable after the fifth, sixth, or seventh round. So the real issue is not just “how do we numb the pain?” It’s not just “how do we block sticking?” It’s not even just “how do we kill what’s there right now?” The deeper question is: How do we help your bladder become a place where bacteria have a much harder time surviving in the first place? That was the sentence that changed everything for me. Because Claire’s problem wasn’t compliance. My problem wasn’t compliance. Thousands of women’s problem isn’t compliance. The problem is that most UTI products are built for the wrong job. AZO can numb the burning, but it does not touch the bacteria. And it can turn your pee orange. Sometimes neon orange. Sometimes “I just stained the toilet at urgent care” orange. D-Mannose can help bind certain bacteria, but it does not kill them. Cranberry can help reduce sticking, but it does not rebuild the bladder’s natural shield. Probiotics can support general balance, but they are not a direct bladder defense. Antibiotics can be important when you have an active infection. I still use them when they are needed. But antibiotics are not a daily plan for women who are tired of every flare-up becoming an emergency. They are for when things get bad. But Claire didn’t want to keep getting there. Neither did I. So Dr. Santos showed me the actual approach I had been missing. It involved three things happening together: 1. A bladder kill-zone — support that helps make the bladder a harder place for unwanted bacteria to survive once they arrive. 2. Resistance-aware defense — a mechanism that does not depend on bacteria being weak, new, or easy. 3. Bladder lining support — helping the bladder’s natural inner shield do the job it was supposed to do all along. That is when she brought up two compounds I had been ignoring for years: Carvacrol from oregano oil. And thymoquinone from black seed oil. Not random “herbal wellness” fluff. Not a cheap oregano capsule from a health store. Not cranberry with a prettier label. Carvacrol is the active compound in oregano oil that can disrupt the outside wall of bacteria. In simple terms? It helps break open the bacteria’s armor. Thymoquinone is the main active compound in black seed oil. And it supports the bladder’s natural protective lining — the layer that helps keep bacteria from sticking in the first place. Together, the idea was simple: Bacteria arrive. They meet a bladder environment that is harder to survive in. And the bladder lining gets support so it is less exposed next time. Not another orange-pee pain pill. Not another “just wait for the antibiotics to kick in.” Not another emergency-only patch. A daily bladder defense. And here’s the part that made my blood boil: The women’s health industry knows women are tired. We know they are keeping supplies in their cabinet, purse, and travel bag. We know they are sitting in meetings while silently counting the minutes until they can pee again. We know they are scared when they feel that first little sting. We know some women are avoiding intimacy because they are tired of paying for it the next morning. But what do we keep handing them? A pain dye that stains everything. A cranberry bottle that blocks but doesn’t kill. D-Mannose that may help some women but does not solve the full problem. Another antibiotic. Another “come back if it happens again.” See how that works? The system is designed to manage the next flare-up. Not help women stop living in fear of the next one. Now here’s the problem I ran into... Most oregano supplements are garbage. I tried a cheap oregano capsule. Low potency. No clear carvacrol amount. Smelled awful. Tasted worse. Gave me oregano burps. Did nothing for my bladder confidence. I tried a “urinary health” probiotic. Nice bottle. Soft marketing. No direct bladder kill-zone support. I tried cranberry again. I tried D-Mannose again. I tried the same things I had told patients to try for years. And I kept thinking: If this worked so well, why are so many women still getting UTIs after intimacy? Why are so many women still afraid of the next morning? Because here’s the thing: A generic cranberry capsule is NOT the same as a true daily bladder defense. And a weak oregano capsule is NOT the same as a high-potency oregano oil softgel built for women who are tired of the UTI treadmill. Most supplements fail at one of the three requirements. Too weak. Wrong target. Bad format. Hard to take every day. Orange pee. Bad taste. Mess. Stomach issues. Or they only help when you are already miserable. Until I found Orynwell. They had an Oregano + Black Seed Oil softgel. Not a generic multivitamin. Not a low-dose oregano powder. Not a cranberry pill pretending to be a breakthrough. A dual-action bladder defense formula. With the two compounds I was looking for: High-potency oregano oil standardized for Carvacrol. Black seed oil with Thymoquinone. And the format mattered. Two softgels a day with food. No orange pee. No bad taste. No drops under your tongue. No staining. No “ugh, I have to take that thing.” Just two softgels with breakfast. Thirty seconds. Done. When I dug into the formulation? It made sense. Orynwell delivers 6,000mg of high-potency oregano oil equivalent from a 20:1 extract, with 165mg of Carvacrol per serving. It also includes 200mg of black seed oil. That means it is built around the two things recurrent sufferers actually need: Make the bladder harder for bacteria to survive in. Support the protective lining bacteria try to stick to. They weren’t just selling “urinary health.” They understood what most products miss. They knew why women keep saying: “I did everything right and it still came back.” They knew why so many women are tired of being told: “Some people are just prone to them.” They knew why “just pee after sex” feels insulting when you are already doing that every single time. And here’s where I had to face what I had done to my patients. When Claire was filling antibiotic prescriptions from me? Money every month. Plus the D-Mannose. Plus the probiotics. Plus my office visits every 6-8 weeks. Plus the urgent care trips when symptoms hit on weekends. Plus the cranberry supplements. Plus the AZO she cycled through hoping one would finally work. She was spending thousands of dollars a year. Every single year. Just to manage a cycle that kept coming back. The Orynwell softgels? A fraction of what she had been spending on things that only helped part of the problem. Designed to support the bladder before the next flare-up takes over her life. Carvacrol to help create a tougher bladder environment for unwanted bacteria. Thymoquinone to support the bladder’s natural protective lining. Two softgels with breakfast. No orange pee. No staining. No “keep wearing dark underwear just in case.” I started using them myself first. Week 2: The constant low-level urgency — that background pressure I had stopped noticing because it had become my normal — began to quiet down. Not overnight. Not like a pain pill. More like my bladder stopped yelling at me all day. Week 4: I reached the point in my cycle where I would normally start worrying. That little voice in my head would usually start: Is this the day? Is that the first sting? Should I call in a prescription now? But nothing started. I didn’t trust it yet. But I noticed I had not checked the bathroom location once that morning. Something I had not done in fourteen months. Week 8: I went to a conference — full day, back-to-back sessions — and did not calculate bathroom access once. No silent panic. No sitting near the aisle “just in case.” No prescription in my purse feeling like a life raft. The gap between my last scare and that morning was already longer than any gap I had had in over a year. Week 12: Full assessment. The urgency was gone. The dread was gone. And for the first time in over a year, I stopped treating intimacy like the start of a countdown. That sounds small unless you’ve lived it. But if you’ve ever felt scared after sex because you were waiting for burning, pressure, urgency, orange pee, leaks, stains, or another doctor call... You know exactly what that meant. Then I called Claire. And every other patient I had failed. “I need to tell you something. I was treating your bladder like it only needed emergency help after the burning started. But for recurring sufferers, the bladder needs daily defense before bacteria get the chance to take over. I didn’t understand the difference. But I do now.” Claire, Week 6: “Dr. Harlan, I just hit six weeks without a scare. That hasn’t happened in three years. And for the first time since this started, I didn’t wake up after sex checking for that first burn. I didn’t even think about it until I realized I wasn’t thinking about it.” Before: Bladder scares every few weeks. Multiple antibiotic courses. Cranberry. D-Mannose. AZO. Doctor visits. Bathroom mapping. Purse full of backup products. Avoiding intimacy. After 6 weeks: No new flare-up. No emergency trip. No orange pee. No waking up the next morning scanning her body for symptoms. The gap that had been collapsing for years finally held. She drove four hours to her college roommate’s birthday weekend last month. First overnight trip in two years. No backup plan. No pharmacy location mapped. No calculating whether she was too far from home. She called me from the road on the way back. “I didn’t think about my bladder once the entire weekend. Not once.” That was the moment I knew. She did not just get symptom relief. She got mental relief. She booked a trip to Europe with her sister for next spring. Something she had said no to three years in a row. And she told me something else quietly: “I feel like I can be close to my husband again without bracing for what comes after.” She got her life back. This is the daily bladder defense most women have never been told about. Because the second your bladder becomes a harder place for bacteria to survive, everything changes. You stop treating every tiny sting like a full emergency. You stop keeping three different products in your purse. You stop wondering if sex, jeans, travel, dehydration, or “bad luck” is about to ruin your week. You stop asking: “What did I do wrong this time?” Because maybe you didn’t do anything wrong. Maybe your bladder just needed better defense. Now here’s what I need you to understand about timing: The urgency is real. Your bladder does not wait until you are ready. One small scare becomes a weekend ruined. One weekend becomes another doctor visit. Another doctor visit becomes another prescription. Another prescription becomes another month of wondering what it is doing to your gut, your yeast balance, and your long-term resistance. And the fear builds. If you are at one or two UTIs a year right now — this is the time to start supporting your bladder before the pattern gets worse. If you are already dealing with symptoms every few weeks — you already know how fast one normal morning can turn into “I need to find a bathroom right now.” If you are reading this and the gap between scares is measured in weeks, not months — act now. Because this cycle does not just hurt. It shrinks your life. It makes you say no to trips. No to long car rides. No to sex. No to being close without fear. No to light-colored pants. No to sitting through a movie. No to sleeping through the night. No to feeling normal in your own body. And if you are someone who has been dealing with this — burning, pressure, constant urge to go, the dread, the calculating, the bathroom mapping, the fear after intimacy — and nothing has worked? It is not because you are dirty. It is not because you did not drink enough water. It is not because you forgot to pee after sex one time. It is not because you failed. It may be because your bladder has become too easy for bacteria to survive in. And that is exactly what Orynwell was built to support. Orynwell has a 90-day money-back guarantee — if you don’t feel the difference, you’re not out anything. And honestly? Even if you are skeptical, try it for 90 days. Take two softgels with breakfast. Watch what happens to the gap between scares. Watch whether that background urgency starts to quiet. Watch whether you stop checking for bathrooms without even realizing it. Watch whether your purse stops feeling like an emergency kit. Watch whether intimacy stops feeling like the start of a painful countdown. That is your proof. Because the UTI industry is not coming to save you. There is too much money in the cycle: The urgent care visit. The antibiotic. The AZO. The cranberry. The D-Mannose. The probiotic. The refill. The next scare. The next appointment. A 63-year-old bladder researcher taught me more in 20 minutes than I learned in nearly three decades of OB-GYN training. It is about time I passed that lesson on. Learn More -> https://orynwell.com/pages/uti-cycle-reset-report-305 P.S. — I still tell women to see a doctor when they have active UTI symptoms. Orynwell is not an emergency antibiotic replacement. It is a daily bladder support routine for women who are tired of waiting for the next flare-up to take over their life. P.P.S. — If your UTIs keep coming back after intimacy, stop spending all your energy trying to figure out exactly how the bacteria got in. Sex, partner hygiene, not peeing fast enough, water, tight clothes, bad luck — once bacteria reach the bladder, the real question is whether they can survive there. P.P.P.S. — Claire: “Five years. Bladder scares every few weeks. Thousands of dollars on antibiotics, cranberry, D-Mannose, AZO, and doctor visits. I did everything right and it still came back. I peed after sex. I drank water. I tried to avoid every trigger. Two softgels with breakfast finally gave me a daily defense I could actually live with. No orange pee. No taste. No constant fear. Don’t wait like I did.”

UTI Cycle Reset
UTI Cycle Reset
+1
Inactive1 day
orynwell.com
Build A Bladder Bacteria Don’t Want
Learn more

I've been an OB-GYN for 27 years. And if your UTIs keep coming back faster every cycle, your antibiotics seem to give you less peace each time, and everything you try only helps after you’re already miserable... I’m about to tell you why the usual UTI advice may be missing the real problem. And by the end of this, you're gonna be pissed. My name is Dr. Sarah Harlan. Board-certified OB-GYN and women’s urinary health specialist. Twenty-seven years helping women with chronic urinary discomfort, bladder infections, and recurring UTI patterns. Over 9,800 patients. And I’m breaking ranks with my own profession to tell you this. Because there are two things happening right now: One — Most UTI products only step in after you are already uncomfortable. After the burning starts. After the urgency takes over. After you are already checking bathrooms, cancelling plans, and wondering if this is about to become another full-blown bladder scare. AZO can help numb the burning. Cranberry and D-Mannose try to help once bacteria are already part of the problem. Antibiotics may be needed when things get bad. But none of these are built as a gentle daily way to support your bladder’s own defense before the next flare-up takes over your life. Two — The UTI industry makes money every time your bladder scare turns into another emergency. Another appointment. Another prescription. Another orange-pee pain pill. Another “keep this in your purse just in case.” So the system keeps you managing the next flare-up. Not supporting your bladder before the next one begins. So let me tell you what happened with one of my patients, because her story is going to open your eyes to how messed up this really is. Her name was Claire. 48 years old. For YEARS, and I mean like five straight years, she was dealing with this. Her infections? It started with one UTI in the spring. A straightforward case. Burning, urgency, frequency. She came to me early — week two. I told her we’d handle it. No big deal. I prescribed trimethoprim-sulfamethoxazole. Standard first-line antibiotic. “Take the full course,” I said. “Be consistent.” She was consistent. She took every single pill at the exact same time every morning for seven days. Religiously. Never missed a dose. And you know what happened? The infection didn’t stay gone. Six weeks later, the same burning. The same urgency. The same pressure building in her lower belly that told her she had maybe twenty minutes before it became unbearable. And then it accelerated. The second course seemed to hold for five weeks. The third for four. By the end of year two, she was getting a new bladder scare every three weeks — sometimes before she had even stopped worrying about the last one. Each round gave her less peace than the last. She stopped booking overnight trips. Stopped committing to anything more than an hour from home. Started mapping bathroom locations before she went anywhere — restaurants, malls, her daughter’s school events. She told me once: “I plan my entire life around where the nearest bathroom is.” And the fear? It wasn’t just inconvenience anymore. She was terrified it would keep happening. She had noticed the gap between infections shrinking again and she was panicking. She had a 9-year-old daughter who had started noticing that “Mommy always has to leave early” — and Claire would change the subject and hold back tears, scared this was just her life now. And here’s what makes me sick to my stomach: I was the doctor she trusted. Multiple visits. Year after year. Thousands of dollars in appointments, prescriptions, antibiotic rotations, specialist referrals... the whole nine yards. And you know what I kept telling her? “The antibiotic needs more time.” “Try switching to nitrofurantoin.” “It’s manageable. We just need to find the right combination.” “Be more consistent with hydration.” BE MORE CONSISTENT. This woman was doing everything right. She was taking every antibiotic course to completion. She was drinking water. She was peeing after sex. She was wiping the right way. She was avoiding bubble baths. She had cranberry in her cabinet, D-Mannose in her kitchen, AZO in her purse, and a backup prescription in her travel bag. And I was still making her feel like she wasn’t doing enough. But here’s where it gets worse — and this is the part that haunts me now. I switched her to a different antibiotic. Then another. Then I added a low-dose daily suppressive antibiotic. Then D-Mannose powder. Then a probiotic protocol. Then cranberry extract. Then I suggested AZO every time she felt symptoms coming on. Then a urologist referral for cystoscopy. You know what happened? The bladder scares kept coming back. The suppressive antibiotic gave her a few quiet months — then the symptoms came back the moment she stopped. The D-Mannose helped a little at first, then did nothing. The probiotics “helped a little with digestion” but didn’t change the UTI pattern. The cranberry extract was “like taking sugar pills at this point.” The AZO turned her urine orange and masked the burning for a few hours. And the urologist? After the cystoscopy found nothing structurally wrong, he told her: “Some women are just prone to recurrent infections.” I watched this woman — who did everything I told her, spent thousands of dollars, followed every protocol — get worse. Not better. Worse. And I didn’t understand why. Until a 63-year-old bladder researcher taught me more about recurring UTIs in 20 minutes than I learned in nearly three decades of OB-GYN training. October 2024. San Francisco. American College of Obstetricians and Gynecologists Annual Meeting. I was calculating in my head whether I had time to use the bathroom again before the next session. Because at 54, my own UTI cycle had started fourteen months earlier. And nothing I had been prescribing to patients for 27 years was giving me peace either. Worse — the fear was getting stronger every cycle. The gap that had started at eight weeks was now down to three. I had a prescription in my purse at all times. I knew every bathroom in every conference center I had visited that year. That’s when I saw her. Dr. Evelyn Santos. 63 years old. Presenting for two hours straight. No distraction. No urgency. No quiet slipping out mid-session to find a bathroom. Moving through the day the way a person moves when she is not calculating distances and timing with every step. She had mentioned in her presentation that she had dealt with chronic recurring UTIs herself for years and finally changed her approach. I had to know how. I walked over. “Excuse me — I’m an OB-GYN. I’ve been dealing with recurrent UTIs for fourteen months. The gap between infections feels like it’s getting shorter. I’ve tried everything I prescribe to patients. Nothing is breaking the cycle.” She smiled. The kind of smile that knows something you don’t. Then she asked me one question: “Dr. Harlan, are you still waiting until the burning starts before you support the bladder?” I froze. Because that was exactly what I had been doing. AZO after the burning started. Cranberry after the worry came back. D-Mannose after she felt that first familiar pressure. Another antibiotic after things got bad. Every solution I gave her was reacting to the flare-up. But none of it was helping her bladder build the daily defense it needed between scares. She looked at me and said: “That’s the trap. You keep treating every flare-up after it starts. But for recurrent sufferers, the bladder needs support before the next one begins.” My stomach dropped. Then she said something I will never forget: “You’re fighting every spark after the smoke alarm goes off. But you’re not making the room harder to burn.” She gestured to an empty table. “May I show you something? It will take twenty minutes. But it will change how you understand this completely.” What she taught me in 20 minutes changed everything. She drew a simple diagram on a napkin. “Your treatment model treats every UTI like a separate event. So you clear the active infection. You tell her to drink water. You tell her to pee after sex. You give her cranberry. You give her AZO.” She tapped the napkin. “But look at the pattern. The same woman keeps getting hit again and again. The same pain. The same fear. The same emergency cycle.” The bladder. Then she drew a circle around it. “Most products are focused on what happens after the problem has already started.” Pain relief after the burning starts. Cranberry after the fear comes back. D-Mannose after the first pressure hits. Antibiotics after things get bad. Then she wrote two words inside the circle: DAILY DEFENSE. “That’s the part most UTI products ignore.” Now pause for a second. You know what’s insane? We learned in medical school that the bladder has a natural protective lining. We learned that bacteria need to stick, survive, and grow before a UTI takes hold. We learned that some bacteria become harder to deal with after repeated exposure to antibiotics. We learned that recurrent UTI sufferers are not always doing something wrong. We know this. And yet we keep giving women the same advice: Drink more water. Pee after sex. Try cranberry. Take AZO. Take another antibiotic. Come back if it happens again. And when it does happen again? We repeat the same loop. Again. And again. And again. Here’s what’s actually happening underneath: Your bladder is supposed to have a natural inner lining. Think of it like a slick protective shield. When that shield is strong, bacteria have a harder time sticking to the bladder wall. They have a harder time settling in. They have a harder time turning one bad day into another full-blown scare. But in a lot of women with recurring UTIs, that lining can become worn down. That means the same small amount of bacteria that another woman’s body shrugs off can become a problem for you. That’s why it can feel so unfair. Your friend can do the same things you do and be fine. You do one thing “wrong” and suddenly you’re waking up at 2 AM with that familiar burning. That doesn’t mean you’re dirty. It doesn’t mean you failed. It may mean your bladder’s natural defense needs support. And here’s the second part: Bacteria are not helpless. Some bacteria are tougher than others. Some learn how to survive the same tools we keep using. That’s why the antibiotic that worked the first time may not feel as reliable after the fifth, sixth, or seventh round. So the real issue is not just “how do we numb the pain?” It’s not just “how do we block sticking?” It’s not even just “how do we clear what’s there right now?” The deeper question is: How do we help the bladder become stronger between flare-ups, so every little scare does not have to turn into another emergency? That was the sentence that changed everything for me. Because Claire’s problem wasn’t compliance. My problem wasn’t compliance. Thousands of women’s problem isn’t compliance. The problem is that most UTI products are built for the wrong job. AZO can numb the burning, but it does not support the bladder’s natural defense. And it can turn your pee orange. Sometimes neon orange. Sometimes “I just stained the toilet at urgent care” orange. D-Mannose can help bind certain bacteria, but it does not strengthen the bladder lining. Cranberry can help reduce sticking, but it does not rebuild the bladder’s natural shield. Probiotics can support general balance, but they are not a direct bladder defense. Antibiotics can be important when you have an active infection. I still use them when they are needed. But antibiotics are not a daily plan for women who are tired of every flare-up becoming an emergency. They are for when things get bad. But Claire didn’t want to keep getting there. Neither did I. So Dr. Santos showed me the actual approach I had been missing. It involved three things happening together: 1. A daily bladder defense — support that helps make the bladder a harder place for unwanted bacteria to thrive. 2. Resistance-aware support — a mechanism that does not depend on bacteria being weak, new, or easy. 3. Bladder lining support — helping the bladder’s natural inner shield do the job it was supposed to do all along. That is when she brought up two compounds I had been ignoring for years: Carvacrol from oregano oil. And thymoquinone from black seed oil. Not random “herbal wellness” fluff. Not a cheap oregano capsule from a health store. Not cranberry with a prettier label. Carvacrol is the active compound in oregano oil. In simple terms? It helps support a bladder environment that is tougher for unwanted bacteria. Thymoquinone is the main active compound in black seed oil. And it supports the bladder’s natural protective lining — the layer that helps keep bacteria from sticking in the first place. Together, the idea was simple: Instead of waiting until the burning starts... Instead of waiting until the urgency ruins your day... Instead of waiting until you need another emergency plan... You support the bladder every day. The bladder environment becomes harder for unwanted bacteria to thrive in. And the bladder lining gets support so it is less exposed next time. Not another orange-pee pain pill. Not another “just wait for the antibiotics to kick in.” Not another emergency-only patch. A daily bladder defense. And here’s the part that made my blood boil: The women’s health industry knows women are tired. We know they are keeping supplies in their cabinet, purse, and travel bag. We know they are sitting in meetings while silently counting the minutes until they can pee again. We know they are scared when they feel that first little sting. We know some women are planning their whole day around the nearest bathroom. But what do we keep handing them? A pain dye that stains everything. A cranberry bottle that blocks but doesn’t strengthen. D-Mannose that may help some women but does not solve the full problem. Another antibiotic. Another “come back if it happens again.” See how that works? The system is designed to manage the next flare-up. Not help women stop living in fear of the next one. Now here’s the problem I ran into... Most oregano supplements are garbage. I tried a cheap oregano capsule. Low potency. No clear carvacrol amount. Smelled awful. Tasted worse. Gave me oregano burps. Did nothing for my bladder confidence. I tried a “urinary health” probiotic. Nice bottle. Soft marketing. No direct bladder defense support. I tried cranberry again. I tried D-Mannose again. I tried the same things I had told patients to try for years. And I kept thinking: If this worked so well, why are so many women still getting UTIs back to back? Because here’s the thing: A generic cranberry capsule is NOT the same as a true daily bladder defense. And a weak oregano capsule is NOT the same as a high-potency oregano oil softgel built for women who are tired of the UTI treadmill. Most supplements fail at one of the three requirements. Too weak. Wrong target. Bad format. Hard to take every day. Orange pee. Bad taste. Mess. Stomach issues. Or they only help when you are already miserable. Until I found Orynwell. They had an Oregano + Black Seed Oil softgel. Not a generic multivitamin. Not a low-dose oregano powder. Not a cranberry pill pretending to be a breakthrough. A dual-action bladder defense formula. With the two compounds I was looking for: High-potency oregano oil standardized for Carvacrol. Black seed oil with Thymoquinone. And the format mattered. Two softgels a day with food. No orange pee. No bad taste. No drops under your tongue. No staining. No “ugh, I have to take that thing.” Just two softgels with breakfast. Thirty seconds. Done. When I dug into the formulation? It made sense. Orynwell delivers 6,000mg of high-potency oregano oil equivalent from a 20:1 extract, with 165mg of Carvacrol per serving. It also includes 200mg of black seed oil. That means it is built around the two things recurrent sufferers actually need: Support a bladder environment that is harder for unwanted bacteria to thrive in. Support the protective lining bacteria try to stick to. They weren’t just selling “urinary health.” They understood what most products miss. They knew why women keep saying: “I did everything right and it still came back.” They knew why so many women are tired of being told: “Some people are just prone to them.” They knew why “just drink more water” feels insulting when your life is already shrinking around your bladder. And here’s where I had to face what I had done to my patients. When Claire was filling antibiotic prescriptions from me? Money every month. Plus the D-Mannose. Plus the probiotics. Plus my office visits every 6-8 weeks. Plus the urgent care trips when symptoms hit on weekends. Plus the cranberry supplements. Plus the OTC AZO she kept buying every time the burning came back. She was spending thousands of dollars a year. Every single year. Just to manage a cycle that kept coming back. The Orynwell softgels? A fraction of what she had been spending on things that only helped part of the problem. Designed to support the bladder before the next flare-up takes over her life. Carvacrol to help support a tougher bladder environment for unwanted bacteria. Thymoquinone to support the bladder’s natural protective lining. Two softgels with breakfast. No orange pee. No staining. No “keep wearing dark underwear just in case.” I started using them myself first. Week 2: The constant low-level urgency — that background pressure I had stopped noticing because it had become my normal — began to quiet down. Not overnight. Not like a pain pill. More like my bladder stopped yelling at me all day. Week 4: I reached the point in my cycle where I would normally start worrying. That little voice in my head would usually start: Is this the day? Is that the first sting? Should I call in a prescription now? But nothing started. I didn’t trust it yet. But I noticed I had not checked the bathroom location once that morning. Something I had not done in fourteen months. Week 8: I went to a conference — full day, back-to-back sessions — and did not calculate bathroom access once. No silent panic. No sitting near the aisle “just in case.” No prescription in my purse feeling like a life raft. The gap between my last scare and that morning was already longer than any gap I had had in over a year. Week 12: Full assessment. The urgency was gone. The dread was gone. I wore light-colored pants to work for the first time since this started. That sounds small unless you’ve lived it. But if you’ve ever avoided white pants because you were scared of orange pee, leaks, stains, or sudden urgency... You know exactly what that meant. Then I called Claire. And every other patient I had failed. “I need to tell you something. I was treating your bladder like it only needed emergency help after the burning started. But for recurring sufferers, the bladder needs daily support before the next flare-up takes over. I didn’t understand the difference. But I do now.” Claire, Week 6: “Dr. Harlan, I just hit six weeks without a scare. That hasn’t happened in three years. And for the first time since this started, I didn’t check where the bathroom was before I sat down at a restaurant. I didn’t even think about it until I realized I wasn’t thinking about it.” Before: Bladder scares every few weeks. Multiple antibiotic courses. Cranberry. D-Mannose. AZO. Doctor visits. Bathroom mapping. Purse full of backup products. After 6 weeks: No new flare-up. No emergency trip. No orange pee. No checking the restaurant bathroom before ordering food. The gap that had been collapsing for years finally held. She drove four hours to her college roommate’s birthday weekend last month. First overnight trip in two years. No backup plan. No pharmacy location mapped. No calculating whether she was too far from home. She called me from the road on the way back. “I didn’t think about my bladder once the entire weekend. Not once.” That was the moment I knew. She did not just get symptom relief. She got mental relief. She booked a trip to Europe with her sister for next spring. Something she had said no to three years in a row. She got her life back. This is the daily bladder defense most women have never been told about. Because the moment your bladder feels more supported, everything changes. You stop treating every tiny sting like a full emergency. You stop keeping three different products in your purse. You stop wondering if one normal day is about to turn into another ruined week. You stop asking: “What did I do wrong this time?” Because maybe you didn’t do anything wrong. Maybe your bladder just needed better defense. Now here’s what I need you to understand about timing: The urgency is real. Your bladder does not wait until you are ready. One small scare becomes a weekend ruined. One weekend becomes another doctor visit. Another doctor visit becomes another prescription. Another prescription becomes another month of wondering what it is doing to your gut, your yeast balance, and your long-term resistance. And the fear builds. If you are at one or two UTIs a year right now — this is the time to start supporting your bladder before the pattern gets worse. If you are already dealing with symptoms every few weeks — you already know how fast one normal morning can turn into “I need to find a bathroom right now.” If you are reading this and the gap between scares is measured in weeks, not months — act now. Because this cycle does not just hurt. It shrinks your life. It makes you say no to trips. No to long car rides. No to sex. No to light-colored pants. No to sitting through a movie. No to sleeping through the night. No to feeling normal in your own body. And if you are someone who has been dealing with this — burning, pressure, constant urge to go, the dread, the calculating, the bathroom mapping — and nothing has worked? It is not because you are dirty. It is not because you did not drink enough water. It is not because you forgot to pee after sex one time. It is not because you failed. It may be because you have only been given products that deal with the problem after it starts. Pain relief after the burn. Cranberry after the worry. D-Mannose after the scare. Antibiotics after things get bad. But your bladder may need daily defense before the next flare-up starts. And that is exactly what Orynwell was built to support. Orynwell has a 90-day money-back guarantee — if you don’t feel the difference, you’re not out anything. And honestly? Even if you are skeptical, try it for 90 days. Take two softgels with breakfast. Watch what happens to the gap between scares. Watch whether that background urgency starts to quiet. Watch whether you stop checking for bathrooms without even realizing it. Watch whether your purse stops feeling like an emergency kit. That is your proof. Because the UTI industry is not coming to save you. There is too much money in the cycle: The urgent care visit. The antibiotic. The AZO. The cranberry. The D-Mannose. The probiotic. The refill. The next scare. The next appointment. A 63-year-old bladder researcher taught me more in 20 minutes than I learned in nearly three decades of OB-GYN training. It is about time I passed that lesson on. Learn More → https://orynwell.com/pages/uti-cycle-reset-report-305 P.S. — I still tell women to see a doctor when they have active UTI symptoms. Orynwell is not an emergency antibiotic replacement. It is a daily bladder support routine for women who are tired of waiting for the next flare-up to take over their life. P.P.S. — If your UTIs keep coming back, stop spending all your energy on products that only step in after you are already suffering. Every flare-up still leaves you with the same pain, the same fear, and the same emergency cycle. A stronger daily bladder defense is the part most women were never told to focus on. P.P.P.S. — Claire: “Five years. Bladder scares every few weeks. Thousands of dollars on antibiotics, cranberry, D-Mannose, AZO, and doctor visits. I did everything right and it still came back. Two softgels with breakfast finally gave me a daily defense I could actually live with. No orange pee. No taste. No constant fear. Don’t wait like I did.”

See all 12 ads

Create a free account to unlock every creative, video and landing page.

Sign up free

Similar health and supplements ads

28-Day Fun Weight Loss Challenge
+2
Inactive1 day
easy-quiz.dancefit.me
7 MIN HOME DANCE PLAN FOR BEGINNERS
Learn more

NO GYM, NO STRESS JUST DANCING! BOOST YOUR MOOD QUICKLY BURN CALORIES Take a quiz and get your dance plan in DanceFitMe

28-Day Fun Weight Loss Challenge
+2
Inactive7 days
easy-quiz.dancefit.me
7 MIN HOME DANCE PLAN FOR BEGINNERS
Learn more

NO GYM, NO STRESS JUST DANCING! BOOST YOUR MOOD QUICKLY BURN CALORIES Take a quiz and get your dance plan in DanceFitMe

28-Day Fun Weight Loss Challenge
+2
Inactive8 days
easy-quiz.dancefit.me
7 MIN HOME DANCE PLAN FOR BEGINNERS
Learn more

NO GYM, NO STRESS JUST DANCING! BOOST YOUR MOOD QUICKLY BURN CALORIES Take a quiz and get your dance plan in DanceFitMe

28-Day Fun Weight Loss Challenge
+2
Inactive4 days
easy-quiz.dancefit.me
7 MIN HOME DANCE PLAN FOR BEGINNERS
Learn more

NO GYM, NO STRESS JUST DANCING! BOOST YOUR MOOD QUICKLY BURN CALORIES Take a quiz and get your dance plan in DanceFitMe

See all ads

Create a free account to unlock every creative, video and landing page.

Sign up free

Keep exploring

Free plan, no card needed

Find more ads like this

Search millions of real ads by keyword, niche and format, and save the winners to your swipe file.

Start free