For eleven years, I told neuropathy patients the same thing. "Surgery can help. Let's talk about your options." And I believed it. I had trained under some of the best peripheral nerve surgeons in the country. I had seen the results. I had watched patients walk differently after decompression — lighter, more confident. I had data that supported the outcomes. I was not a negligent doctor. I was an incomplete one. And the difference between those two things cost my patients years of suffering I could have shortened — if only I had understood what I'm about to share with you. I want to start with a number. According to surgical outcome data on peripheral neuropathy decompression, somewhere between thirty and fifty percent of patients report no significant improvement one year after surgery. One in three. Sometimes one in two. These aren't surgical failures in the traditional sense. No infections. No complications. The nerves were decompressed exactly as planned. Postoperative imaging looks clean. The surgery worked. The patient didn't get better. For years, the explanation we gave those patients was: nerves are slow to heal. Give it more time. Manage your symptoms in the meantime. But the truth — the truth I found only after years of digging through neuroscience literature that nobody was assigning in surgical training programs — is that for a significant portion of neuropathy patients, compression is only one part of the problem. And the other part is one that no scalpel can reach. Let me tell you about Raymond. Raymond was fifty-four years old. A former long-haul truck driver who had spent decades sitting behind a wheel, lower body compressed for eight to twelve hours at a stretch, irregular meals, poor sleep, the kind of life the body slowly files complaints about until they become impossible to ignore. His complaints came in the form of his feet. Numbness first. Then tingling. Then burning that he described as putting on socks full of sand every morning. His EMG showed clear compression along the posterior tibial nerve. His podiatric neurologist had been recommending tarsal tunnel release surgery for over a year. Raymond had been avoiding it. He came to my office for a second opinion. I reviewed his imaging. I reviewed his nerve conduction studies. I told him surgery was a reasonable option. That in patients with his profile, decompression had good odds of meaningful improvement. He asked me, point blank: "Doc, is surgery going to fix this?" I told him it would give his nerves the best chance to recover. He had the surgery. Fourteen months later, he was back in my office. The numbness had not resolved. The burning had shifted locations — moved up into his shins. His hands were starting to show early signs of involvement. "You said this would give my nerves a chance," he said. He wasn't angry. Raymond wasn't that kind of man. But there was something in his voice — a specific exhaustion that I have never been able to stop hearing — that told me he had been holding onto hope for over a year and had just watched it run out. I sat across from him and I didn't have an answer. That night, I made a decision. I was going to find out what was happening in the nerve cells of patients like Raymond. Not in the gross anatomy. Not in the structures we can decompress and release and reshape. Inside. At the level no surgical instrument can address. I spent the next four months doing almost nothing else. And I found a paper that changed the way I understand neuropathy entirely. It was published in a European neurological research journal, authored by a team studying post-decompression outcomes in peripheral neuropathy patients. Their finding: *"In patients with established peripheral neuropathy, chronic mitochondrial impairment within peripheral nerve axons creates an energetic deficit that persists following surgical decompression. Nerve regeneration requires substantial ATP production — a demand that cannot be met in metabolically compromised nerve tissue, regardless of structural decompression."* I read it three times. Then I read the supporting literature. Then I understood what I had missed for eleven years. Peripheral neuropathy, by the time it is symptomatic enough to recommend surgery, has almost always been active long enough to damage the mitochondria — the energy-producing structures inside nerve cells — through chronic oxidative stress, inflammation, and circulatory impairment. These mitochondria are responsible for producing ATP. Adenosine triphosphate. The fuel that nerve cells run on. The fuel that powers remyelination — the rebuilding of the protective sheath around nerve fibers that makes clean signal transmission possible. Without adequate ATP production, the nerve cannot repair its myelin. The signal stays broken. The symptoms persist. And the critical part — the part that explains Raymond, and Margaret, and hundreds of patients like them — is that surgical decompression does nothing to restore mitochondrial function. It removes the structural pressure. It does not touch the energy deficit. So the nerve, finally freed from compression, tries to regenerate. Reaches for the resources to rebuild myelin. And finds the cupboard empty. We gave the body an opportunity it didn't have the resources to take. I thought about Raymond for a long time after I understood this. And then I started looking for something that could address the problem we'd been leaving on the table. I found it through a colleague I had known since residency — a neurologist who had quietly left hospital practice to work in functional medicine, specifically with patients who had failed to improve after standard neurological interventions. When I described what I'd been reading about mitochondrial dysfunction in peripheral nerve, he said, "Yes. I know exactly what you're describing. And I've been working with something that addresses it." He told me about Methylene Blue. I was skeptical. Methylene Blue is a compound I associated with IV treatment in very specific clinical emergencies. It was not something I had ever considered in the context of chronic neuropathy management. He walked me through the mechanism slowly. Methylene Blue, at appropriate doses, functions as a direct electron carrier in the mitochondrial transport chain. It can step in where damaged mitochondrial complexes have failed and carry electrons through to ATP production through an alternative pathway. What that means in practice: it gives nerve cells access to energy production that the normal, damaged pathway can no longer reliably provide. On top of that, it is one of the most well-documented antioxidants for neural tissue — directly quenching the reactive oxygen species that have been burning through nerve fibers and Schwann cells for years. And it creates favorable conditions for remyelination — the biological process of nerve repair that requires ATP and a low-oxidative-stress environment simultaneously. He said: "What you've been doing surgically is removing the obstacle. What this does is give the nerve the resources to actually move through it. You need both." I spent several weeks corroborating everything he told me. The research was consistent. The mechanism was sound. The outcomes in early clinical work with neuropathy patients were exactly what the mechanistic model predicted. But there was a practical problem. Methylene Blue in therapeutic form was not something neuropathy patients could easily, safely, or reliably access. Pharmaceutical solutions were designed for very different clinical applications. Dose consistency was poor in the products that existed. Bioavailability was inconsistent. Until I saw what Boovelle had developed. A team with deep roots in neuroscience research had built a formulation designed specifically for this application. They had solved the bioavailability problem. They had built in dose consistency. And they had delivered it in a format — a daily gummy — that patients could actually sustain as part of a long-term protocol. Boovelle™ Methylene Blue Gummies. Not a gimmick. Not a general wellness product. A targeted formulation built around the specific biological mechanism I had spent months trying to find. I recommended it to Raymond. He called me ten weeks later. He said the burning had dropped significantly. That he was sleeping better. That the sand-in-the-socks feeling had softened enough that mornings weren't something he dreaded anymore. Twelve weeks after that, he sent me a photo. He was standing at the finish line of a 5K charity walk. His grandson was beside him. He had completed the entire course. I called him the next day. "I thought the surgery was going to give me my life back," he said. "It didn't. This did." I'm not saying surgery is wrong. There are patients for whom decompression is genuinely the right intervention, and I still perform it. But I am saying that if surgery is being presented to you as the answer to peripheral neuropathy — if you are sitting across from a doctor who has not discussed mitochondrial function, oxidative nerve damage, or the energetic requirements of nerve regeneration — you are not getting the full picture. And you deserve the full picture before you make this decision. Right now, Boovelle is running a 40% off promotion, with a full 60-day money-back guarantee. Nothing to lose. Two months to find out whether addressing the root energy deficit changes what's possible for your nerves. https://boovelle.com/products/boovelle%E2%84%A2-methylene-blue-gummies For eleven years, I sent patients into operating rooms without giving them this information. I can't undo that. But I can make sure the next person who's considering neuropathy surgery hears what Raymond never did before he went in. Your nerves are not broken because of pressure alone. They are starving at the cellular level. And until that starvation is addressed, no surgery can deliver what you're hoping it will.
Dr. Victoria Whitmore Facebook and Instagram ad
Dr. Victoria Whitmore ran this image ad since Jun 25, 2026, 135 days so far, targeting United Kingdom.
Ad copy
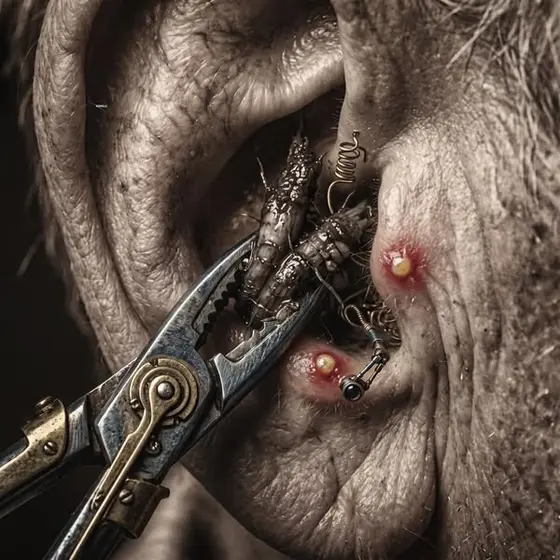
If you hear a high-pitched ringing in your ears, your inner ear cells are being destroyed right now — and you are running out of time. Look at the image above. I know it is disturbing. I know you would rather look away. But if you have been living with that constant, relentless ringing in your ears, you need to understand what you are actually looking at. That is not a diagram. That is not a medical illustration from a textbook. That is a visual of what is happening inside your cochlea at this very moment. Your inner ear hair cells are being burned alive. Not by heat. By oxidative fire. Microscopic, unstoppable, cellular destruction happening in complete silence — except for that ringing. That ringing is not a sound. That ringing is your body's distress signal. It is the sound of thousands of irreplaceable cells misfiring, shorting out, and dying — one by one. And by the time you finish reading this, you are going to be furious. Because the answer has been sitting in your own cells this entire time. And the medical industry has known about it for decades. --- My name is Karen. And for three years, I was not living. I was surviving. It started the way it always does. A faint, high-pitched tone. Barely there. The kind you notice only when the room goes completely quiet. I told myself it was nothing. I told myself it was stress. I told myself it would pass. It did not pass. It grew. Week by week, month by month — it climbed in volume like someone was slowly turning up a dial inside my skull that I could not reach. By the end of year one, it was a steady, piercing whine. By year two, it was a screaming electrical tone that lived in my head every hour of every day. I stopped going to restaurants. Too quiet between the noise. I stopped going to bed before midnight. Darkness made it worse. I stopped being able to hold a conversation without the ringing drowning out half of what the other person was saying. My husband thought I was ignoring him. My children thought something was wrong with me. Something was wrong with me. But nobody could see it. Nobody could hear it. Nobody could understand it. Because the loudest sound in my world was completely invisible to everyone around me. I went to my doctor. He looked in my ears, nodded slowly, and said the two words I will never forget. "It's tinnitus." I said, okay — so what do we do? He leaned back in his chair and said, "We manage it." He did not say fix it. He did not say cure it. He said manage it. He referred me to an audiologist who quoted me $3,500 for a pair of masking devices — little machines that play white noise directly into your ear canal to distract you from the ringing. Not to stop the ringing. To distract you from it. I drove home in tears. I was not going to spend $3,500 to be distracted from my own suffering. I was going to find the real answer. --- So I did what every desperate person does. I started reading. Everything I could find. Medical journals. Academic papers. Foreign clinical studies. Research that had been published, buried, and never followed up on. And what I found changed everything. Here is what nobody tells you about the ringing in your ears. Your inner ear contains thousands of microscopic hair cells — tiny, delicate sensory receptors that convert sound vibrations into electrical signals that travel to your brain. These cells are extraordinarily sensitive. And they have one deadly enemy. Oxidative stress. Every single day, your cells generate free radicals as a byproduct of normal biological activity. Your body is supposed to neutralize those free radicals with antioxidants — specifically with a molecule called Glutathione. Glutathione is your body's master antioxidant. Your cells produce it naturally. It is the primary defense system that protects your neurons, your inner ear hair cells, and your entire auditory pathway from oxidative destruction. But here is the problem. By the time you reach your thirties, your body's ability to produce Glutathione starts declining. Every year after that, levels drop further. Add in chronic stress. Processed food. Environmental toxins. Alcohol. Medications. And your Glutathione levels collapse. When Glutathione disappears, the oxidative fire starts. The free radicals that were supposed to be neutralized begin attacking your most vulnerable cells — and your inner ear hair cells are among the first to go. They do not regenerate. Once they die, they are gone. And as they die in clusters, misfiring their last signals on the way out — you hear ringing. The ringing is not tinnitus. The ringing is a cellular obituary. Your body telling you that your inner ear is under attack and losing. And here is what terrified me most. Recent research has connected this same pattern of oxidative nerve damage to accelerated cognitive decline. The same process that destroys your inner ear hair cells does not stop there. It creeps along the auditory nerve, into the brainstem, and into the memory-processing centers of the brain. Your ears and your mind are losing the same war. And nobody told you. --- But I also found the solution. If the problem is glutathione depletion — the answer is restoring glutathione. Simple. Except it is not that simple. Because oral glutathione supplements — the kind you find in any pharmacy — are almost completely useless. Glutathione is a fragile molecule. The moment it hits your stomach acid, it is destroyed before it ever reaches your bloodstream. You are swallowing an expensive molecule that your digestive system annihilates before it can do a single thing. This is what the supplement industry does not want you to know. Standard glutathione supplements have a bioavailability rate so low it is functionally pointless. But there is a delivery technology that changes everything. Liposomal encapsulation. Liposomes are microscopic phospholipid spheres — the same material your cell walls are made from. When glutathione is wrapped inside a liposome, it survives the digestive tract completely intact. It passes directly into your bloodstream. It crosses the blood-brain barrier. And it reaches your inner ear hair cells and auditory nerve with its full potency. This is not a theory. This is a delivery mechanism used in pharmaceutical drug delivery for decades. Applied to glutathione — it turns an otherwise useless supplement into a genuine neurological repair tool. When your inner ear cells are finally receiving the glutathione they have been starved of — the oxidative fire begins to cool. The cellular destruction slows. The misfiring signals quiet. And the ringing begins to fade. This is not masking the symptom. This is addressing the biological cause. --- When I understood this, I went looking for a liposomal glutathione that was formulated specifically for neurological and auditory repair. Not a generic antioxidant blend. Not a multivitamin with trace amounts of everything. A clinical-grade, high-concentration liposomal glutathione designed to actually reach the cells that needed it. I tried four different products over six months. Three of them were garbage — poor liposomal quality, low concentration, fillers, artificial ingredients. And then I found Radiance Liposomal Glutathione Drops. A small company. No flashy marketing. No celebrity endorsements. Just a clinically-formulated, high-potency liposomal glutathione in sublingual liquid drops — administered directly under the tongue to achieve maximum absorption before it even hits the stomach. The formula bypasses digestive destruction entirely. Straight into the bloodstream. Straight to the brain. Straight to the inner ear. I ordered two bottles. I started taking it the same night. --- The first three days — nothing. I expected nothing. I told myself to be patient. Day five — I noticed I had slept past 3:00 AM for the first time in months. I did not know if it was the glutathione or exhaustion. I kept going. Day nine — I was lying in bed in the dark and realized the ringing, while still present, seemed slightly further away. Like someone had placed a thin piece of glass between me and the sound. Week two — it was quieter. Noticeably, undeniably quieter. I was almost afraid to acknowledge it in case I was imagining it. Week three — my husband asked me why I seemed calmer. I told him I thought the ringing was getting better. He looked at me like he was afraid to believe me. By the end of week four, I sat in our kitchen at 11:00 PM in complete silence. And I heard the refrigerator hum. I heard the faint sound of traffic from the road outside. I heard my own breathing. I did not hear the ringing. I sat there for twenty minutes, completely still, waiting for it to come back. It did not come back. I put my face in my hands and sobbed. Not because I was sad. Because I had forgotten that this was possible. --- That was nine months ago. I have taken Radiance Liposomal Glutathione Drops every single day since. The ringing has not returned. Not a whisper. Not a trace. I sleep through the night. I go to restaurants. I hear my children's voices clearly when they call me from the other room. I got my life back. Not by masking the sound. Not by distracting myself from the torture. By actually extinguishing the oxidative fire that was destroying my inner ear — cell by cell — while my doctor told me to just accept it. --- I need you to understand something. Your inner ear hair cells are dying right now. Every day you wait, more of them die. Every day the glutathione depletion continues, the oxidative damage spreads further along the auditory nerve. And the medical establishment will not tell you any of this. Because liposomal glutathione cannot be patented. Because a supplement cannot be sold for $3,500. Because the entire masking-device industry collapses if the cellular cause of tinnitus is treated directly. They have every financial reason to keep you suffering. And you have every reason to stop. --- Go to the link below right now. See if Radiance Liposomal Glutathione Drops are still in stock. This is not a mass-produced supplement. Production is limited. And when word spreads, they sell out fast — sometimes for weeks. If they are available when you click, do not hesitate. Every day that passes is more cellular damage. Every night of lost sleep is another night your body tried to heal without the tool it needed. They offer a complete money-back guarantee. You have nothing to lose except the ringing. You deserve silence. Real silence. Not a white noise machine pretending to give it to you. Click below. Right now. Before they sell out. Before another night passes. https://tryqurella.com/products/qurella%E2%84%A2-liposomal-glutathione-drops
Placements and targeting
More ads from Dr. Victoria Whitmore
I've performed over three hundred nerve decompression surgeries in my career. And for years, I believed it was the right answer. Remove the tissue compressing the nerve, restore the signal, and the symptoms disappear. That's what every neurology textbook teaches. But after enough years in practice, something started to bother me. Patients I operated on would return months later still burning. Still numb. Still dropping things. Still stumbling across their own living room. The incisions healed. The nerves didn't. And no one could tell me why. I remember one patient clearly. A retired pharmacist named Gerald. Forty-two years standing behind a counter, measuring pills, walking on hard tile floors, bending over prescription pads under fluorescent lights. He came to me unable to feel his feet properly. Every step felt like walking on broken glass. Classic peripheral neuropathy. We did the decompression surgery. It went exactly as planned. Eight weeks later he came back and said, "The burning is still there, Doctor. I thought removing the pressure would fix it." I told him nerves heal slowly. That six months was still too early to judge. Six months later, he said the numbness had spread to his calves. That his hands were starting to tingle at night. That was the day I started questioning everything I thought I knew. If nerve compression was the real problem, surgery should fix everyone. But it didn't. So why were so many patients still deteriorating — even after we removed the pressure? That question kept me up at night. I started reading every study I could find. Late nights. Cold tea beside my notes. The same thought repeating over and over... What are we actually missing? Then I found it. It was buried in a neuroscience publication from a research institute in Zurich. It read: "Peripheral nerve regeneration is not limited by compression alone. The primary bottleneck is mitochondrial dysfunction within the nerve cell itself — an energy deficit that leaves nerves biologically incapable of repair." I read it four times. The real problem wasn't just external pressure on the nerve. It was what was happening inside the nerve cells themselves. Your nerve fibers require enormous amounts of cellular energy — ATP — just to maintain their signals. And years of damage, inflammation, and poor circulation slowly destroy the mitochondria inside those nerve cells. Like letting the battery in a flashlight drain completely — and then wondering why it won't turn on even after you fix the switch. The nerves don't just get damaged. They go dark. So even if you surgically release the compression, the nerve cells are still energetically starved. Still unable to regenerate myelin — the protective sheath that wraps each nerve fiber. Still unable to carry signals properly. It finally made sense. We were replacing the light socket while the battery was already dead. Once I understood that, I started searching for something that could restore energy production inside nerve cells. Something non-invasive. Something the body could actually use to begin repairing from the inside out. That's when a colleague — a functional medicine physician who worked primarily with diabetic neuropathy patients — mentioned something he'd been quietly using with results he couldn't explain any other way. He said, "It's not a drug or an injection. It's a compound that's been studied for over a century — and most neurologists have never heard of it in this context." I almost dismissed him. But then he showed me the research. Methylene Blue. A compound that acts as a mitochondrial electron carrier — meaning it steps directly into the energy production process inside cells and restores what years of nerve damage had depleted. He walked me through exactly what it does that nothing else addresses together: First: It donates electrons directly to the mitochondrial transport chain.** Essentially jump-starting ATP production in nerve cells that had gone energetically dark. Second: It neutralizes the oxidative stress burning through nerve tissue.** The same oxidative fire that keeps neuropathy patients awake at three in the morning with their feet on fire. Third: It supports myelin synthesis.** Helping rebuild the protective sheath around nerve fibers — the sheath that makes clean signal transmission possible in the first place. He said, "The reason people don't get better is that we only address one piece at a time. Drugs mask the pain signal. Surgery removes the compression. But neither one gives the nerve cell the raw energy it needs to actually repair itself. And without that energy, nothing else works." That stopped me cold. Because he was right. I spent the next three months going through every clinical paper I could find on Methylene Blue and neurological function. The data was consistent. Improved mitochondrial efficiency. Reduced oxidative nerve damage. Measurable improvement in nerve regeneration markers. It was the biological opposite of what I'd been doing in the operating room. Instead of cutting away tissue from the outside, it restored what the nerve had lost at the cellular level. But I ran into one problem. Most Methylene Blue products on the market were pharmaceutical-grade liquids — designed for hospital use, not daily neuropathy support. Others came in forms with poor bioavailability, or dosing so inconsistent that patients had no idea what they were actually getting. Until a few months later, when that same colleague sent me a link. "You need to see what this company built," he said. That's how I found Boovelle. A health company that partnered with neuroscience researchers and formulation specialists — several of them neuropathy patients themselves — who had spent years trying to solve this exact problem. They developed a precise delivery format that could get therapeutic levels of Methylene Blue into the system consistently, safely, and daily — without the complexity of pharmaceutical liquids or the unreliability of standard capsules. They called it **Boovelle™ Methylene Blue Gummies.** For the first time, it wasn't a clinical compound locked behind a hospital setting. It was formulated specifically for people living with neuropathy — and built to address the root mechanism I had spent years trying to understand. So I tried it myself. As a surgeon, I'm on my feet for hours, bending under bright operating lights. Years of this had left my own hands with occasional tingling after long procedures — something I had quietly learned to accept. I took two gummies in the morning and started paying attention. Within ten days, the tingling I'd normalized had noticeably reduced. By the end of four weeks, it was gone. I couldn't dismiss that. So I began recommending it to patients who were either trying to avoid surgery — or who hadn't responded to surgery the way the textbooks said they should. One of them, a retired nurse who had lived with diabetic neuropathy for eleven years, came back after six weeks and said, "Dr. Whitmore, I wore real shoes yesterday. For the first time since 2019, I wore actual shoes." Another patient — a grandfather who'd been afraid to walk his dog at night because he couldn't trust his own feet — told me he'd just completed a two-mile walk without stopping. That's when I stopped treating these results as coincidences. When you give nerve cells the energy to repair — and reduce the oxidative load that's been burning them down — the nervous system knows exactly what to do. It just needed the raw material. I still perform surgery when it's genuinely the right answer. I'm not anti-surgery. But I'm no longer willing to operate on a neuropathy patient without first asking: have we addressed the cellular environment these nerves are trying to heal in? You can't cut your way to nerve regeneration. You have to restore the conditions that make regeneration biologically possible. That's why I now recommend Boovelle™ Methylene Blue Gummies — not because of marketing, but because it addresses the mechanism I spent years trying to find. It restores mitochondrial function in nerve cells. It reduces the oxidative stress that keeps nerves from recovering. It gives the nervous system the building blocks it needs to begin rebuilding myelin. And when you do that — when you finally give depleted nerve cells what they've been starved of — the body's capacity for healing can begin to express itself again. I'm not sharing this as a sales pitch. I've watched too many patients spend years on gabapentin — losing their mental sharpness, losing their balance — without ever being told that the underlying energy problem in their nerve cells wasn't being addressed at all. If you've been told that the burning, the numbness, the tingling — that this is just something you manage for the rest of your life — please, ask a harder question before you accept that answer. Right now, Boovelle is offering **40% off** — with a full **60-day money-back guarantee.** No risk. No fine print. Just the option to find out for yourself. Here's the link. https://boovelle.com/products/boovelle%E2%84%A2-methylene-blue-gummies No pressure. Just the science I wish someone had handed me years ago — before I ever picked up a scalpel. Sometimes healing doesn't begin in the operating room. Sometimes, it begins in the cell.
I've had patients come to me after neuropathy surgery who were worse than when they went in. Not slightly worse. Noticeably, measurably, undeniably worse. And for a long time, I didn't have an honest answer for why. I trained for over a decade to perform nerve decompression surgeries. Tarsal tunnel release. Peroneal nerve release. Lumbar nerve root decompression. These are real procedures. I'm good at them. And in the right patient, under the right conditions, they matter. But something nobody told me in my training — and nobody told those patients before they went under — is that surgery cannot fix what surgery didn't break. And in peripheral neuropathy, surgery almost never addresses the thing that's actually broken. I want to explain what I mean. Because I think it might be the most important thing a neuropathy patient can hear before making any decision about their care. Let me start with Margaret. She was a sixty-one-year-old school librarian. Twenty-eight years of sitting at a reference desk, helping students, quiet work that didn't look stressful from the outside. But her feet told a different story. By the time she found my office, she'd been living with burning, stabbing pain in both feet for three years. Nighttime was the worst — she'd described lying in bed with her feet on fire, unable to sleep more than two hours at a stretch. Her previous neurologist had ordered an EMG and nerve conduction study. The results showed reduced signal velocity in the peroneal and sural nerves. The recommendation was surgical decompression — release the fibrous tissue compressing the nerve at four points in each leg. Margaret asked me if she should do it. I told her yes. And I still think about that conversation. She had the surgery. Both legs. Bilateral decompression. It was technically clean. No complications. The tissue was released exactly as planned. Ten weeks post-op, she came back for her follow-up. "It's worse," she said. She didn't say it dramatically. She said it the way someone says something when they've already accepted a terrible thing. Quietly. Like a door closing. The burning had spread from her feet to her ankles. Her fingertips had started tingling. She was dropping her keys. I ordered new nerve conduction studies. The compression was gone. I could see that. But the nerve function wasn't better. In some measurements, it had declined further. The surgery had done everything it was supposed to do. And the patient was still deteriorating. That's when I spent the first of many nights unable to sleep, turning the same question over and over: If the compression was the problem, and we removed the compression, why is she getting worse? I started pulling research. Not clinical guidelines — actual bench science. Neuroscience papers. Cellular biology journals. And I found something that should be taught in every medical school that trains surgeons who operate on nerves. It came from a research group at the University of Copenhagen. They had been studying why peripheral nerve regeneration so frequently stalls — even in cases where the structural cause of compression had been successfully addressed. Their conclusion: *"Mitochondrial dysfunction within the Schwann cells and axons of damaged peripheral nerves creates an energetic deficit that prevents remyelination, regardless of whether external compression has been relieved."* I read that sentence and felt the floor shift under me. Myelination — the rebuilding of the protective sheath around nerve fibers — is a metabolically expensive process. It requires enormous quantities of cellular energy. ATP. Produced by mitochondria inside the nerve cells and the support cells that wrap them. And years of neuropathy — the inflammation, the oxidative stress, the poor circulation — quietly destroys that mitochondrial function long before a surgeon ever makes an incision. So when the patient goes in for decompression, the nerve is already energetically bankrupt. The compression is real. The surgery addresses the compression. But the nerve cells are still running on empty. They don't have the biological resources to begin repairs. The structural problem was fixed. The energetic problem was never identified. Never addressed. Never even discussed. Think of a construction crew sent to rebuild a collapsed bridge. You remove the rubble. You clear the site. But if you send a crew with no tools, no materials, no fuel — nothing gets built. That's what we were doing. We cleared the rubble. We sent in an empty crew. And then we told patients to give it time. Once I understood this, I couldn't operate the same way anymore. I started asking: before we discuss surgery, what can we do to restore the metabolic environment inside these nerve cells? Because if we go in surgically without addressing the energy deficit, we may relieve compression while the nerves remain biologically incapable of healing. That question led me, after months of research, to something I had never encountered in my surgical training. A colleague who specialized in integrative neurology — someone who had spent fifteen years working with post-surgical neuropathy patients who hadn't improved — described a compound he'd been incorporating into his protocols. He said, "I know how it sounds. But the mechanism is real. Look at the electron transport chain literature." He was talking about Methylene Blue. Not a drug in the traditional sense. A compound that has been studied in biomedical science for over a hundred years, increasingly recognized for one specific property that is directly relevant to neuropathy: it acts as an alternative electron carrier in the mitochondrial transport chain. In plain language, it bypasses the damaged steps in a nerve cell's energy production process — and helps the cell generate ATP through a different pathway, even when the normal machinery is compromised. That's not a metaphor. That's the documented biochemistry. He walked me through the three things it does that nothing else addresses together: **It restores mitochondrial energy production in nerve cells.** Not by stimulating the damaged system, but by carrying electrons through an alternative route. Giving the nerve cell fuel it can actually use. **It neutralizes free radical damage in nerve tissue.** The oxidative stress that has been burning through nerve fibers for years — attacking myelin, disrupting signaling, killing Schwann cells — gets interrupted at the molecular level. **It supports the biological conditions needed for remyelination.** When the energy crisis is relieved and the oxidative environment is calmed, the cells responsible for rebuilding myelin can finally do their job. He said, "The reason your post-surgical patients don't improve is that you successfully removed the compression, but the nerve cells still can't produce enough energy to rebuild. This gives them that energy." I spent six weeks going through every paper I could find. The mechanistic data was solid. The results in early clinical work were consistent: improved nerve conduction velocity, reduced pain scores, measurable improvement in nerve regeneration markers. It was addressing the problem underneath the problem. But availability was an issue. Most Methylene Blue formulations were pharmaceutical solutions designed for IV use or specific clinical applications — not accessible, not appropriate for daily neuropathy support, and not formulated for consistent bioavailability. Until my colleague showed me what Boovelle had built. A team that included neuroscience researchers and formulators who had dealt with neuropathy personally — not just professionally — had spent years developing a form that could deliver Methylene Blue in a reliable, daily-use gummy format with the consistency and bioavailability that the clinical research required. Boovelle™ Methylene Blue Gummies. Not another supplement with a long ingredient label and vague claims. A targeted formulation designed specifically around the mitochondrial mechanism in peripheral nerve cells. I tried them myself. Years of surgical work had left me with intermittent hand tingling that I'd normalized as occupational reality. Within three weeks, the tingling was measurably reduced. By week six, I had forgotten it had been there. Then I started recommending them — carefully, selectively — to post-surgical neuropathy patients who hadn't responded the way the textbooks said they should. Margaret was one of the first. She came back after eight weeks. "The burning is quieter," she said. Still quietly. But this time it wasn't a door closing. It was something opening. By the four-month mark, she was sleeping through the night. A retired firefighter I'd operated on two years prior — bilateral tarsal tunnel, minimal post-surgical improvement — told me he'd started cooking again. His hands had been too unreliable to hold a knife safely. Now he was making Sunday dinners for his grandchildren. I am not telling you surgery is never the answer. I am telling you that surgery without addressing the cellular energy environment of the nerve is, in many cases, an incomplete answer. And for some patients, it makes things worse — not because the surgeon failed, but because the underlying mechanism was never the compression alone. Before you go into an operating room for a neuropathy procedure, please ask: what is being done to support mitochondrial function in my nerve cells? What is being done to address the oxidative damage that years of neuropathy has caused inside those nerve fibers? If nobody has asked that question, you haven't had the full conversation. Right now, Boovelle is offering 40% off, backed by a full 60-day money-back guarantee. No risk. No commitment beyond two months. Just the chance to find out whether addressing the root biological mechanism makes a difference for you — before, or instead of, anything more invasive. https://boovelle.com/products/boovelle%E2%84%A2-methylene-blue-gummies I've stood at an operating table and done everything right — and watched patients walk out still suffering. I'm not willing to keep doing that without offering them this piece of the puzzle first. Because sometimes the nerve doesn't need a scalpel. It needs a reason to believe it can repair itself. And that reason starts at the cellular level.
If that ringing in your ears has been getting louder — stop what you are doing and read this now. Because what I am about to show you is not something your doctor learned in medical school. It is not something the hearing industry wants you to find. And it is the only thing that actually stopped the screaming inside my head after three years of hell. --- My name is Mike. I am 54 years old. I spent 28 years as an electrician. Crawling through walls. Running wire through concrete. Wearing ear protection on the loud jobs and forgetting it on the short ones. I figured the ringing was just the price of the trade. A buzzing in the left ear after a long day. You get used to it. Except I never got used to it. Because it never went away. That quiet buzz turned into a tone. That tone turned into a high-pitched whine that started following me home. Into the house. Into the bedroom. Into my sleep. Or what was left of my sleep. By the end of year two, I was waking up four times a night. Not because of pain. Not because of noise from the street. Because the noise was inside my own skull and I could not escape it. My wife started sleeping in the guest room. Not because I snored. Because I would get up at 2:00 AM and pace the kitchen floor like a trapped animal, trying to exhaust myself back into unconsciousness. I became someone I did not recognize. Short-tempered. Scattered. Exhausted in a way that sleep did not fix — because the sleep never came. My foreman started asking if I was alright. I told him I was fine. I was not fine. I went to my GP. He sent me to an ear specialist. The specialist ran a hearing test, told me I had some high-frequency hearing loss — completely expected for someone in my trade — and handed me a pamphlet about sound therapy devices. He told me tinnitus was permanent. He told me the ringing would likely get worse with age. He told me my best option was learning to redirect my attention away from it. I have worked with my hands my entire adult life. I have never walked away from a broken circuit without fixing it. I was not going to walk away from this one. --- I started researching on my own. Nights I could not sleep, instead of staring at the ceiling, I started reading. And what I found in those early morning hours — buried in clinical papers and neuroscience journals that most people will never read — turned my frustration into fury. Here is the truth about tinnitus that nobody in that specialist's office told me. The ringing is not a hearing problem. It is a cellular damage problem. Deep inside your inner ear, you have thousands of microscopic hair cells — sensory receptors so delicate they can detect vibrations smaller than the diameter of a single atom. These cells are your hearing. They convert sound into electrical signals that travel to your brain. And they have one mortal enemy. Oxidative stress. Your body produces free radicals every single day — unstable molecules that attack and destroy surrounding tissue. Under normal conditions, your body neutralizes them with its master antioxidant: Glutathione. Glutathione is produced naturally inside every cell in your body. It is the primary shield that protects your neurons, your auditory pathways, and your inner ear hair cells from oxidative destruction. But here is what changes everything. After your mid-thirties, your body's glutathione production begins declining — roughly 10 to 15 percent per decade. Stack on top of that: decades of noise exposure, chronic stress, inflammation, processed food, environmental toxins — and your glutathione levels collapse. When glutathione disappears, the oxidative fire has nothing to stop it. It moves into the most vulnerable territory first. And your inner ear hair cells — irreplaceable, non-regenerating — are among the first casualties. As they die, they misfire. They send garbled, erratic signals to the brain. And the brain, receiving this electrical static, interprets it the only way it can. As sound. That high-pitched tone you cannot escape? That is the sound of your inner ear burning. Cell by cell. Hour by hour. Night after night. And the terrifying part — the part that made me sit up straight at 3:00 AM and feel ice in my stomach — is that the research does not stop at the ear. The same oxidative cascade that destroys your hair cells does not respect boundaries. It travels up the auditory nerve. Into the brainstem. Into the regions responsible for memory and cognitive processing. The scientific literature connecting untreated auditory oxidative damage to accelerated cognitive decline is substantial. Your ears and your brain are fighting the same losing battle. And you are losing it faster every single day you do nothing. --- But I also found the answer. If the problem is glutathione depletion — you restore the glutathione. That logic is straightforward. The execution is not. Here is what the supplement industry buries in fine print. Oral glutathione — the capsules and tablets you find at any health food store — is almost completely useless in standard form. Glutathione is a fragile tripeptide molecule. The moment it contacts stomach acid, it is broken apart and destroyed before a meaningful amount ever reaches your bloodstream. Studies on standard oral glutathione show a bioavailability so low it barely registers. You are paying for a molecule your body destroys before it can do anything. But there is a solution that the pharmaceutical world has used for years in drug delivery. Liposomal encapsulation. A liposome is a microscopic sphere made from phospholipids — the same material that forms your cell membranes. When glutathione is encapsulated inside a liposome, it survives the digestive environment completely intact. It passes into the bloodstream. It crosses the blood-brain barrier. And it arrives at your inner ear hair cells and auditory neurons with its full potency — delivering exactly what those dying cells have been starved of. This is not speculation. Liposomal delivery is a documented, peer-reviewed pharmaceutical technology. Applied to glutathione, it transforms a supplement your body destroys into one your body can actually use. When your inner ear cells finally receive adequate glutathione — the oxidative damage slows. The misfiring quiets. The electrical static begins to clear. The ringing starts to fade. Not because the sound is masked. Because the cellular fire causing it is finally being extinguished. --- Once I understood the mechanism, I went looking for the right product. Not a cheap, underdosed glutathione capsule. Not a generic antioxidant complex with trace amounts of everything. A clinical-grade, high-concentration liposomal glutathione with documented absorption rates and a delivery method that bypassed digestive destruction entirely. I found Radiance Liposomal Glutathione Drops. Sublingual liquid drops — administered directly under the tongue. Absorbed through the mucous membranes directly into the bloodstream, before stomach acid gets involved at all. High-potency. Clean formula. No fillers. No binders. No garbage. Just the molecule my inner ear had been begging for, delivered in a form my body could actually absorb. I ordered two bottles and told myself to be patient. --- Week one — nothing dramatic. I was not looking for a miracle. I was looking for a signal. Day eight — I noticed I had slept past 4:00 AM. First time in months. Day eleven — the ringing was still there, but it felt fractionally quieter. Like someone had turned the dial down by the smallest amount. I almost dismissed it as wishful thinking. I kept going. Week two — my wife came into the kitchen one morning and said I looked different. More rested. I did not tell her why. I was not ready to say it out loud yet. Week three — I was sitting in my truck at lunchtime and I realized I had not thought about the ringing once that morning. Not because I was distracted. Because it was quieter. End of week four. I sat in my garage at 10:00 PM with the lights off and the door closed. The only sound I could hear was the distant bark of the neighbor's dog. I sat very still for a long time. Waiting for the whine to return. It did not return. I am not a man who cries easily. I sat in that dark garage and let out the longest breath I think I have ever exhaled. Three years of that sound. And it was gone. --- It has been eleven months. I take Radiance Liposomal Glutathione Drops every morning. The ringing has not come back. Not a trace. I sleep six, seven hours straight. I wake up rested for the first time in years. I am back on the job sites. I am back in my head. My wife told me last week she has her husband back. I do not share that easily. But if you are sitting there right now, in the dark, listening to that noise that no one else can hear — I want you to know it does not have to be permanent. Not if you address the actual cause. Not if you give your inner ear cells what they need to stop the damage. --- The ringing in your ears is not a life sentence. It is a warning. Your inner ear is burning through its antioxidant reserves. The cells are dying. And every day you wait, more of them are gone. Permanently. Go to the link below now. Check if Radiance Liposomal Glutathione Drops are still in stock. When this gets out — and it is getting out — supply disappears fast. They back it with a full money-back guarantee. You have nothing to lose. Except the ringing. Click below before they sell out. https://tryqurella.com/products/qurella%E2%84%A2-liposomal-glutathione-drops
Similar health and supplements ads
NO GYM, NO STRESS JUST DANCING! BOOST YOUR MOOD QUICKLY BURN CALORIES Take a quiz and get your dance plan in DanceFitMe
Keep exploring
Find more ads like this
Search millions of real ads by keyword, niche and format, and save the winners to your swipe file.